
Cochlear implant debate
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Build and defend a claim-evidence-reasoning position on whether cochlear implants should be standard care for deaf children.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
- • A cochlear implant converts sound to electrical signals that stimulate the auditory nerve, bypassing damaged hair cells.
- • The Deaf community debate centers on identity and consent, not just clinical outcome.
- • A CER requires a falsifiable claim, specific evidence, and reasoning that connects them.
Resistance genes ride on plasmids that bacteria pass sideways through conjugation, , and transduction, so a susceptible cell can become multi-drug resistant in one transfer, which is why superbugs spread resistance faster than alone ever could.
A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
Driving question: Should a cochlear implant be standard care for a deaf infant when the surgery works best before age two, before the child can say yes or no?
What you already know: Resistance genes ride on plasmids that bacteria pass sideways through conjugation, , and transduction, so a susceptible cell can become multi-drug resistant in one transfer, which is why superbugs spread resistance faster than alone ever could.
New idea: A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
Visual or model: No figure is attached to this lesson. The readings, the worked example and E1 to E3 carry the evidence.
- Observe or measure the relevant feature in cochlear implant debate.
- Organize the observation with a stable evidence ID.
- Apply this rule: Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: Should a cochlear implant be standard care for a deaf infant when the surgery works best before age two, before the child can say yes or no?
What the evidence supports: E1 to E3 support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
- • : The spiral, snail-shaped part of the inner ear that turns sound vibrations into nerve signals the brain reads as hearing.
- • : A sensory cell in the inner ear with tiny hair-like bundles that convert sound vibrations or movement into nerve signals the brain can read.
- • : A graph from a hearing test that plots the softest sounds a person can hear at different pitches, showing the type and degree of any hearing loss.
- • : A preparation that delivers an (or the instructions to make one) so the immune system learns to recognize the real later.
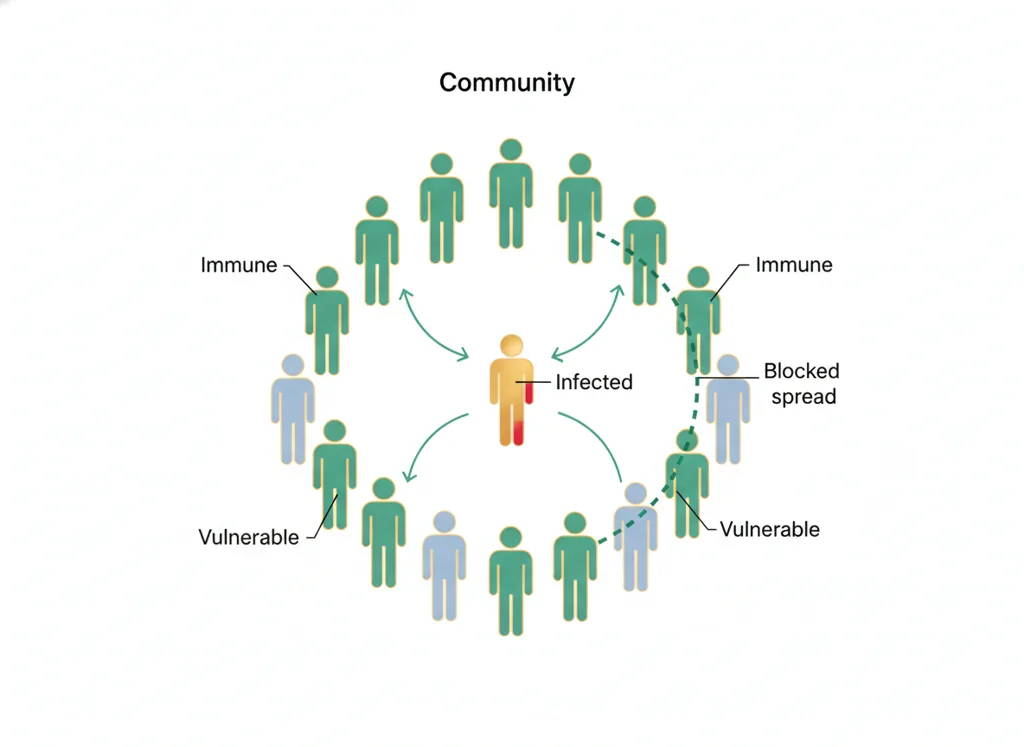
- • : Protection that arises when enough people in a community are immune to a disease that its spread slows and shields those who are not immune.
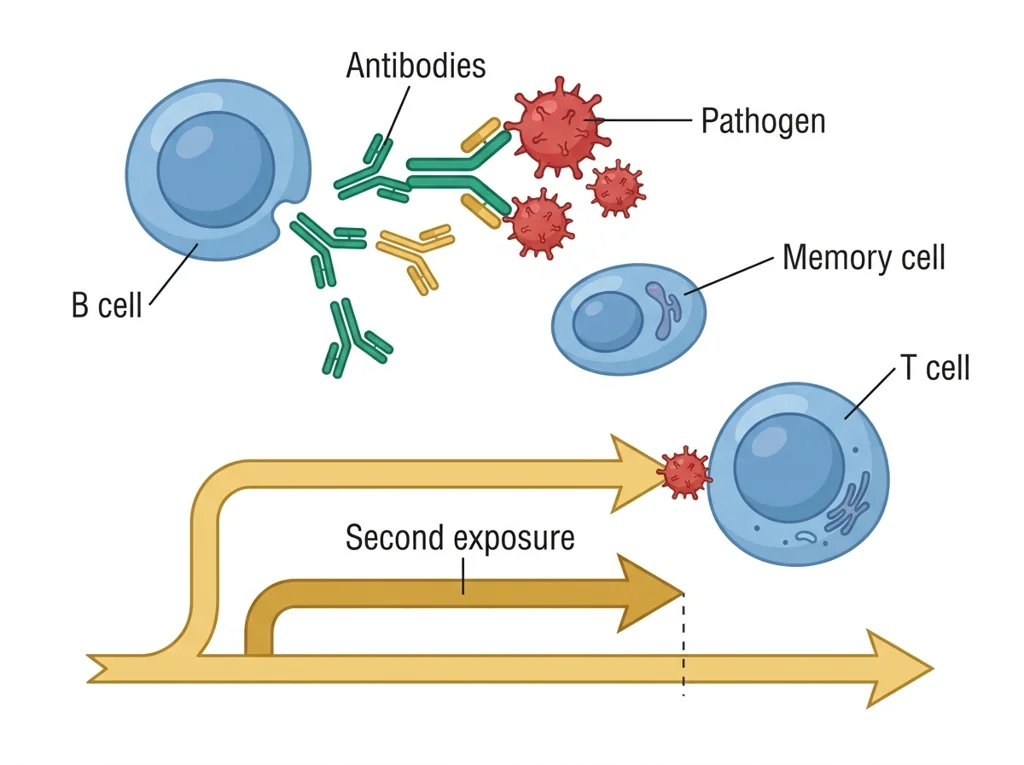
- • : The part of the immune system that learns a specific , builds targeted antibodies and memory cells, and responds faster the next time it appears.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
A defensible biomedical decision separates scientific evidence from value judgments, identifies who may benefit or be burdened, and states the uncertainty and tradeoffs that remain.
Limit: Scientific evidence can inform the options and likely consequences, but it cannot choose a single value-neutral answer.
Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
Limit: A review-board model organizes reasoning but does not make one ethical principle automatically outweigh every other principle.
You can state a defensible claim about cochlear implants backed by evidence.
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: medical interventions team member
Decision: Your team must decide what the evidence from cochlear implant debate supports before submitting the claim-evidence-reasoning response named on today's page.
- • Recommend the implant for every deaf infant, since it restores normal hearing and refusing it means refusing an obvious cure.
- • Ask what the family and deaf adults say about benefit and burden before defending either side of this claim.
- • Treat the implant decision as ethical as well as clinical, because an infant cannot consent to a claim about normal.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about cochlear implant debate. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from cochlear implant debate supports before submitting the claim-evidence-reasoning response named on today's page.
Context: A medical intervention is never only a clinical choice; it also carries a claim about what counts as normal, and the people living inside that claim have a stake in the decision.
- • T1: Read the printable case summary in Part 2 of this page before you write anything. If myPLTW opens, you may also read the Activity 1.3.3 brief, but the summary is enough to do today's work.
- • T2: Write two prepared debate questions that get at the ethics of changing a child's hearing.
- • T3: Draft one CER contribution: a claim about cochlear implants, two pieces of evidence, and your reasoning.
- • T4: In the live debate, listen for one opposing point and note how it challenges your reasoning.
- • T5: Submit your CER and a three-sentence reflection on what changed your mind as one PDF in Schoology.
- • E1: A defensible biomedical decision separates scientific evidence from value judgments, identifies who may benefit or be burdened, and states the uncertainty and tradeoffs that remain.
- • E2: Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
- • E3: You can state a defensible claim about cochlear implants backed by evidence.
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Students often think a cochlear implant restores normal hearing, so refusing it looks like refusing an obvious cure. The trap: An implant does not restore normal hearing; it converts sound to electrical signals that stimulate the auditory nerve, and the brain has to learn to read a signal that is coarser than natural hearing. Treating it as a simple cure hides the real question, which is about identity and consent, not just decibels.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.
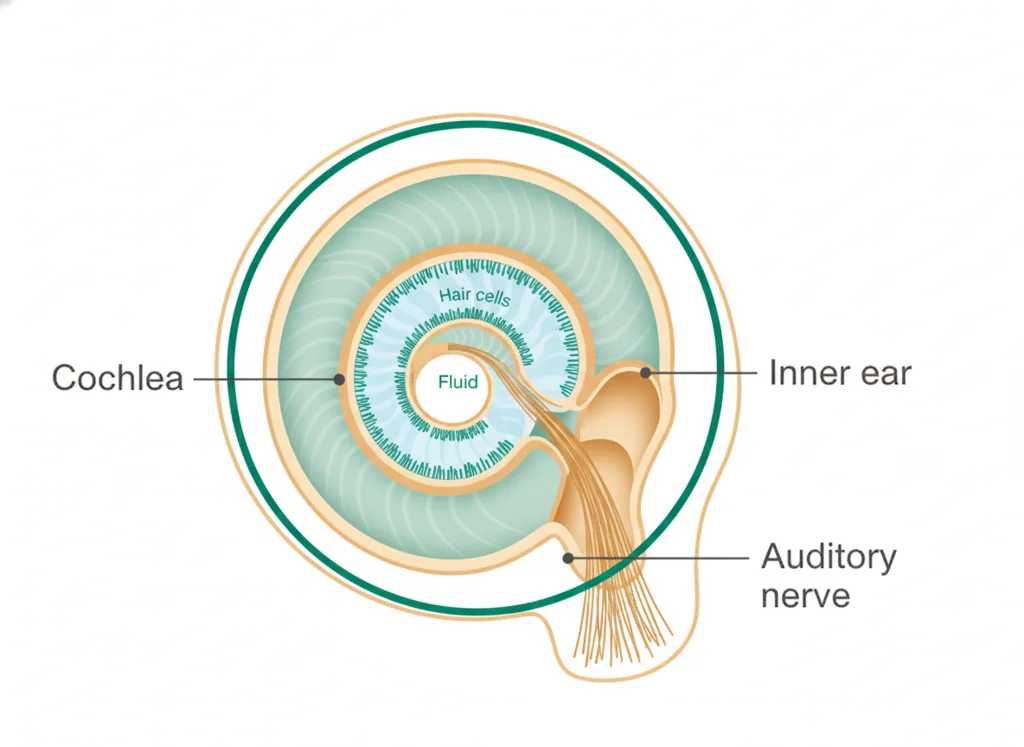
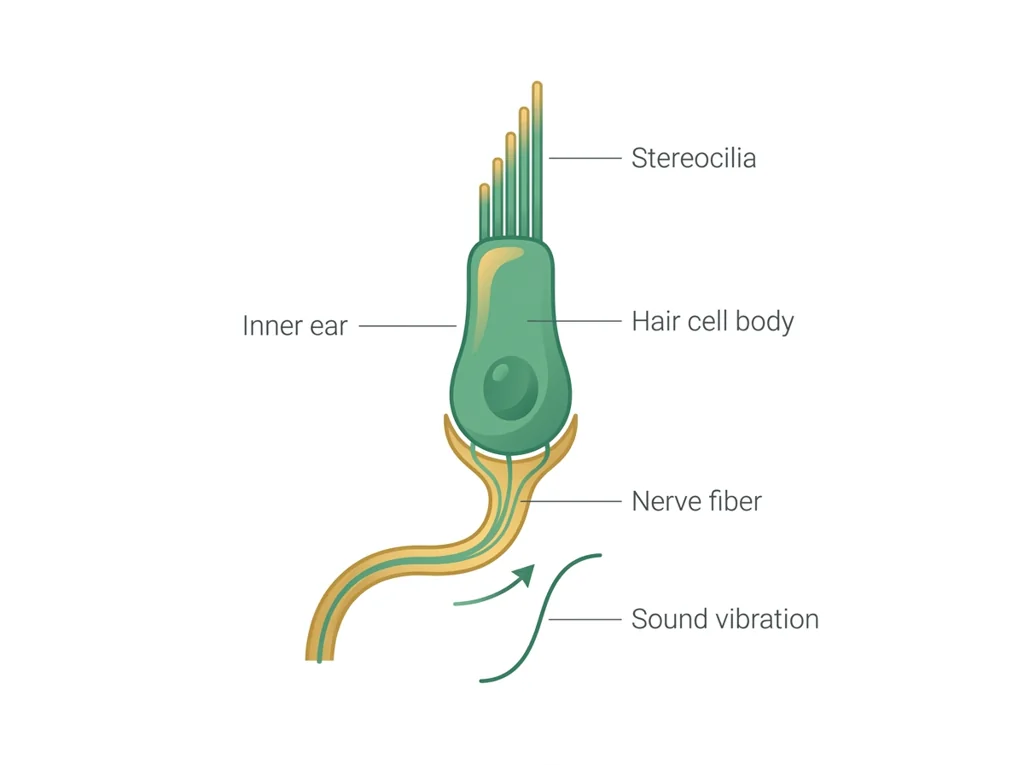
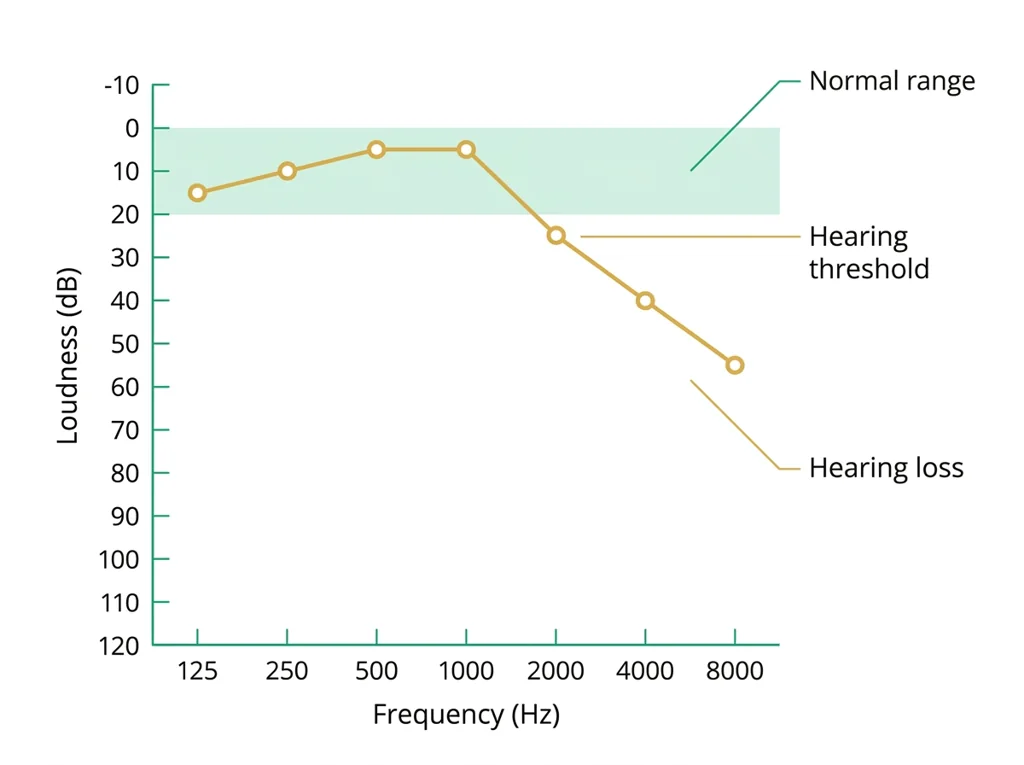
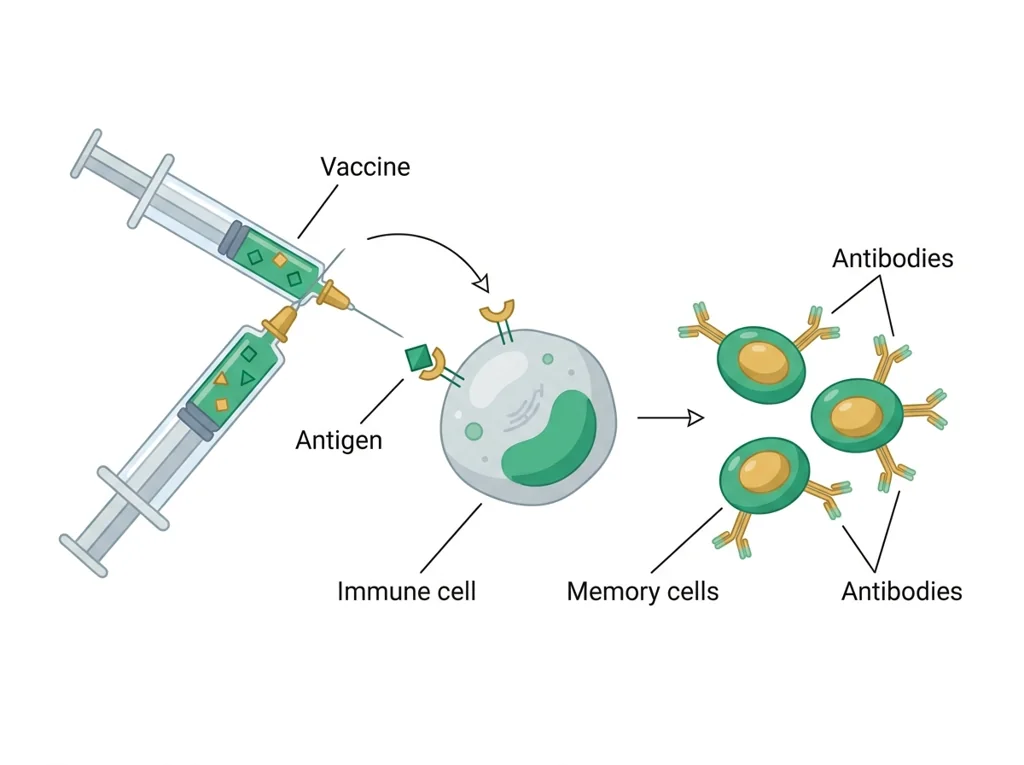
Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Cochlear implant debate. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
Printable case summary: a cochlear implant decision (a made-up family, written for this class)
The family
- Baby R. is a healthy 8-month-old in Cleveland who was born deaf in both ears. Newborn hearing screening flagged it, and an audiologist confirmed it.
- The care team says Baby R. is a candidate for cochlear implants, and the surgery can be done once the baby is 9 months old.
- One parent wants the implants as soon as possible, so the baby has access to sound during the years when spoken language develops fastest.
- The other parent grew up Deaf and uses American Sign Language. This parent says being Deaf is a language and a community, not an illness, and wants Baby R. raised in sign language first and free to decide about an implant later.
What the implant does and does not do (NIDCD, Cochlear Implants)
- A cochlear implant has an outside part that sits behind the ear, with a microphone and a speech processor, and an inside part placed under the skin by surgery, with electrodes that reach the hearing nerve.
- It skips the damaged part of the ear and stimulates the hearing nerve directly. A hearing aid only makes sound louder for the ear that is already there.
- It does not restore normal hearing. It gives a useful version of sound, and it takes surgery plus a lot of therapy to learn to use it.
- Since 2020 the FDA has approved implants for eligible children starting at 9 months old. Hearing sound while very young gives a child a better window for learning spoken language.
The decision
- Should Baby R. get cochlear implants now, before the child can agree or refuse, or should the family wait?
- For your CER: make one claim, use two pieces of evidence from this summary, and explain how the evidence supports the claim. Name who carries the risk if your claim is wrong.
2.2 Start the work
Read the printable case summary in Part 2 of this page before you write anything. If myPLTW opens, you may also read the Activity 1.3.3 brief, but the summary is enough to do today's work.
Show all 5 required steps
- Read the printable case summary in Part 2 of this page before you write anything. If myPLTW opens, you may also read the Activity 1.3.3 brief, but the summary is enough to do today's work.
- Write two prepared debate questions that get at the ethics of changing a child's hearing.
- Draft one CER contribution: a claim about cochlear implants, two pieces of evidence, and your reasoning.
- In the live debate, listen for one opposing point and note how it challenges your reasoning.
- Submit your CER and a three-sentence reflection on what changed your mind as one PDF in Schoology.
Lost your place? Reread the printable case summary in Part 2 of this page. If you have read it, your next move is to draft your CER: one claim, two pieces of evidence, and your reasoning, then post it with a three-sentence reflection.
- 0-5Hook audio demo and framing question
- 5-20Silent read of cochlear implant case brief; draft two debate questions
- 20-35CER draft: claim, evidence x2, reasoning
- 35-65Structured debate: two rounds, affirmative and negative positions
- 65-75Individual written reflection (what changed your mind?)
- 75-80Submit CER and reflection in Schoology; teacher closes
- • Hook: Play 10 seconds of audiologist-recorded speech at 70 dB loss, then at normal volume.
- • Why it matters: Cochlear implant decisions are made for infants who cannot consent, and they are irreversible.
- • Today's debate uses some hearing background, like decibels and hearing thresholds, that you will practice formally with the on Thursday, October 8.
- • Today's structure: 5 min case brief, 15 min prep, 30 min structured debate, 10 min reflection, 10 min post.
- • Exit goal: Your CER and reflection posted before the bell.
PLTW connection and today's work
Open the cochlear implant debate activity in myPLTW for Lesson 1.3 The Aftermath, Hearing Loss, specifically Activity 1.3.3 Cochlear Implants, and review the CER rubric.
Today's stopping point: Project 1.2.3 Attack of the Superbugs (culturing) should be submitted; this is your first Lesson 1.3 benchmark.
PLTW activity titles identify the course connection. If your account will not open, use the posted materials for today and tell Mr. Mendoza. Do not mark an online activity complete unless you completed it.
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
Parallel case (not today's prompt): Should a genetic screen for a serious adult-onset condition that has no childhood treatment be added to the standard newborn screening panel that every baby receives at birth?
Claim: A genetic screen for an untreatable adult-onset condition should be offered to parents as an optional add-on, but it should not be folded into the automatic newborn screening panel that every baby receives.
Evidence 1: Standard newborn screening tests a heel-prick blood sample for a set list of conditions, and the panel was built mostly around disorders that can be treated early, such as PKU, where starting a special diet in the first weeks prevents brain damage.
Evidence 2: A result for an adult-onset condition with no childhood treatment does not change the infant's care now, but it creates lifelong knowledge about that person's future body that the newborn cannot yet weigh, and that some people later say they would have chosen not to learn.
Reasoning: Because the automatic panel earns its automatic status by catching problems that early action can fix, adding a test that changes nothing in childhood breaks that logic and hands a child a permanent result they never agreed to receive. Offering the screen as a clearly separate choice keeps the medical benefit available for families who want it while protecting the future adult's right to decide what to know about their own body.
Reflection: At first I assumed more information at birth is always better, so screening for everything seemed obviously good. Thinking about the difference between a result you can act on now and a result the child will carry for decades made me see that timing and consent matter, not just the test's accuracy. I kept my claim that the screen should exist, but moved it out of the automatic panel and into an informed, opt-in choice.
This model shows the level of evidence and organization needed to complete: Parallel model showing the full CER format: a claim on whether an untreatable-condition genetic screen should be added to the newborn panel, two pieces of evidence, reasoning, and a three-sentence reflection. Students copy the structure, not the answer.
- Write one defensible claim.
- Choose specific evidence that supports the claim.
- Explain the scientific rule that connects the evidence to the claim.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Post your CER and reflection to Schoology before the end of the block.
A review board sorts scientific evidence, stakeholder needs, possible benefits, possible burdens, and uncertainty before choosing a policy.
- Which statements are scientific evidence?
- Which statements express a value or priority?
- Who receives the benefit and who carries the burden?
Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
A review-board model organizes reasoning but does not make one ethical principle automatically outweigh every other principle.
- • Evidence cards map to source-backed findings.
- • Stakeholder cards map to affected people and priorities.
- • The recommendation maps to an explicit tradeoff with a named uncertainty.
Part 4 of 4 · Your work▸
Check your work before submitting
- You'll be able to state a defensible claim about cochlear implants backed by evidence.
- You'll be able to respond to an opposing argument without dismissing it.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- One CER (claim, two evidences, reasoning) on cochlear implant ethics plus a three-sentence reflection.
How to submit and name your file
Submit the CER and the reflection as one PDF in Schoology.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Find this lesson's Schoology assignments
These are existing assignments for your section. Follow the directions in the assignment you are working on; this list does not add new work. A PLTW Work row repeats on every day of its lesson; submit it once. Check Schoology for each deadline.
- Wk7 CER: Cochlear implant debate(today's turn-in)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: Resistance genes ride on plasmids that bacteria pass sideways through conjugation, transformation, and transduction, so a susceptible cell can become multi-drug resistant in one transfer, which is why superbugs spread resistance faster than mutation alone ever could. Today: A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about cochlear implant debate. It cannot prove causation, diagnose a real patient, or justify action outside this room.
A parent says, 'The implant will fix my baby's hearing so she is normal like everyone else.' Rewrite that sentence so it is medically accurate about what the implant does.
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
If you missed the live debate, read the printable case summary in Part 2 of this page, then submit a written CER (claim, two pieces of evidence, reasoning) plus your two debate questions and a short reflection as one PDF in Schoology.
Submit the CER and the reflection as one PDF in Schoology.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
NIH MedlinePlusSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Classroom documents for this lesson are posted in Schoology. Open Clever, then Schoology, and find each one by the name shown on its card.
Use this with the vaccination lesson to connect development to a real example.
Use this if you were absent, got stuck, or need another pass before you submit the lesson artifact.
Use this if you were absent, got stuck, or need another pass before you submit the lesson artifact.
Open this when the class reaches this activity and use it to complete the required lesson artifact.
Sign in to Clever with your district Microsoft account to open Schoology or myPLTW. Follow today's posted steps. If myPLTW will not open, use the posted alternative and tell Mr. Mendoza. Turn in your completed work through the Schoology assignment.
This week
My Progress dashboard