
Audiogram interpretation
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Read an audiogram to describe the type and severity of a patient's hearing loss using decibel and frequency language.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: The plots louder thresholds farther down the chart so that a lower line reads as worse hearing, which lets a clinician classify severity and predict which range of speech sounds is likely to be hardest to hear.
- • axes: frequency (Hz, low-to-high left-to-right) and threshold (dB HL, increasing downward).
- • The speech banana spans roughly 500-4000 Hz at 25-65 dB, covering most conversational sounds.
- • Degree of loss is set from the pure-tone average of the 500, 1000 and 2000 Hz thresholds, one ear at a time: normal (up to 25 dB HL), mild (26 to 40), moderate (41 to 55), moderately severe (56 to 70), severe (71 to 90), profound (91 and above). Where the loss is worse by frequency is described separately.
A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
The plots louder thresholds farther down the chart so that a lower line reads as worse hearing, which lets a clinician classify severity and predict which range of speech sounds is likely to be hardest to hear.
Driving question: Given a patient whose thresholds sit at 15 dB in the low frequencies but drop to 65 dB at 4000 Hz, which everyday sounds fall out of their world, and is this loss mild, moderate, or severe?
What you already know: A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one.
New idea: The plots louder thresholds farther down the chart so that a lower line reads as worse hearing, which lets a clinician classify severity and predict which range of speech sounds is likely to be hardest to hear.
Visual or model: No figure is attached to this lesson. The readings, the worked example and E1 to E3 carry the evidence.
- Observe or measure the relevant feature in interpretation.
- Organize the observation with a stable evidence ID.
- Apply this rule: A decision is stronger when the test fits the question and its limits are known.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: Given a patient whose thresholds sit at 15 dB in the low frequencies but drop to 65 dB at 4000 Hz, which everyday sounds fall out of their world, and is this loss mild, moderate, or severe?
What the evidence supports: E1 to E3 support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
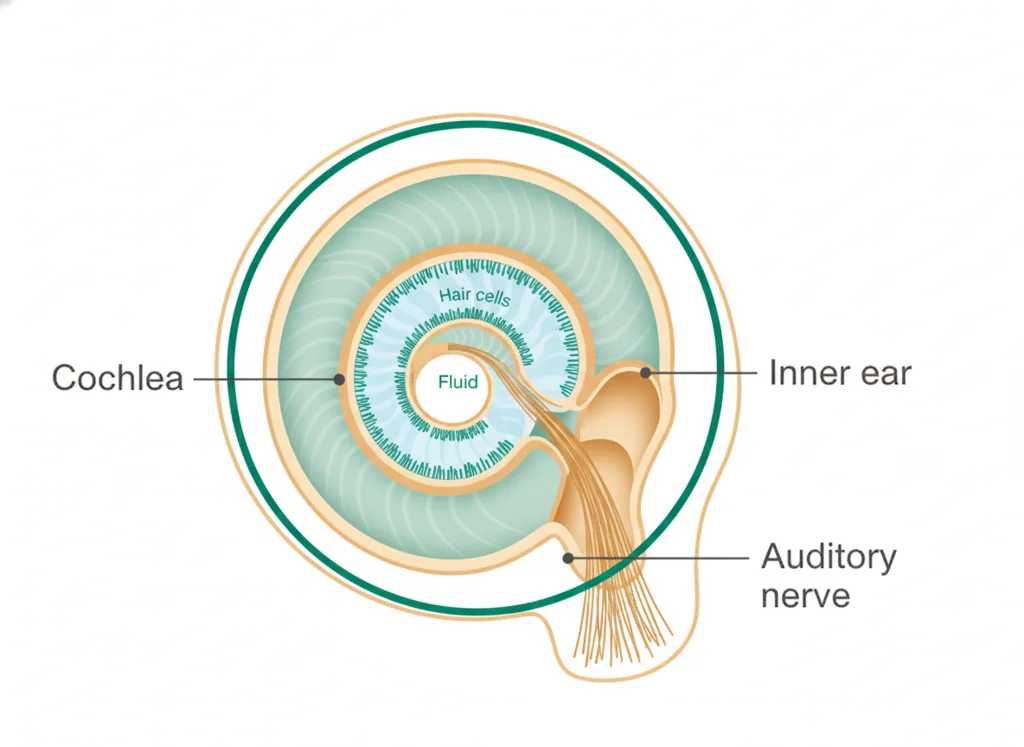
- • : The spiral, snail-shaped part of the inner ear that turns sound vibrations into nerve signals the brain reads as hearing.
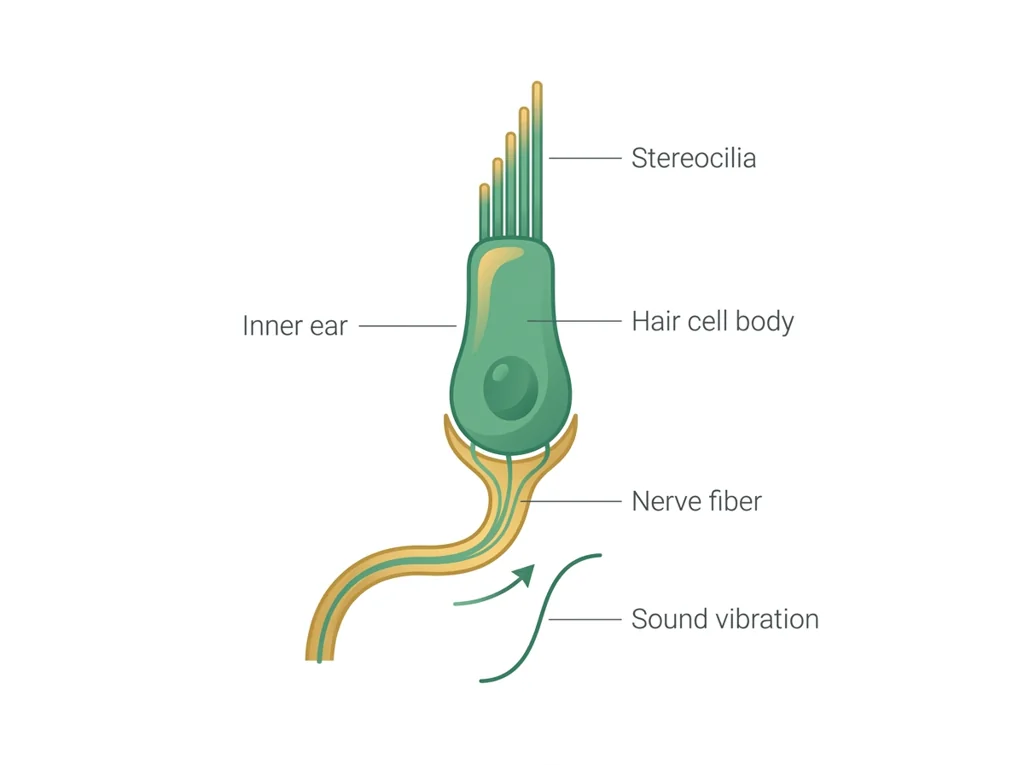
- • : A sensory cell in the inner ear with tiny hair-like bundles that convert sound vibrations or movement into nerve signals the brain can read.
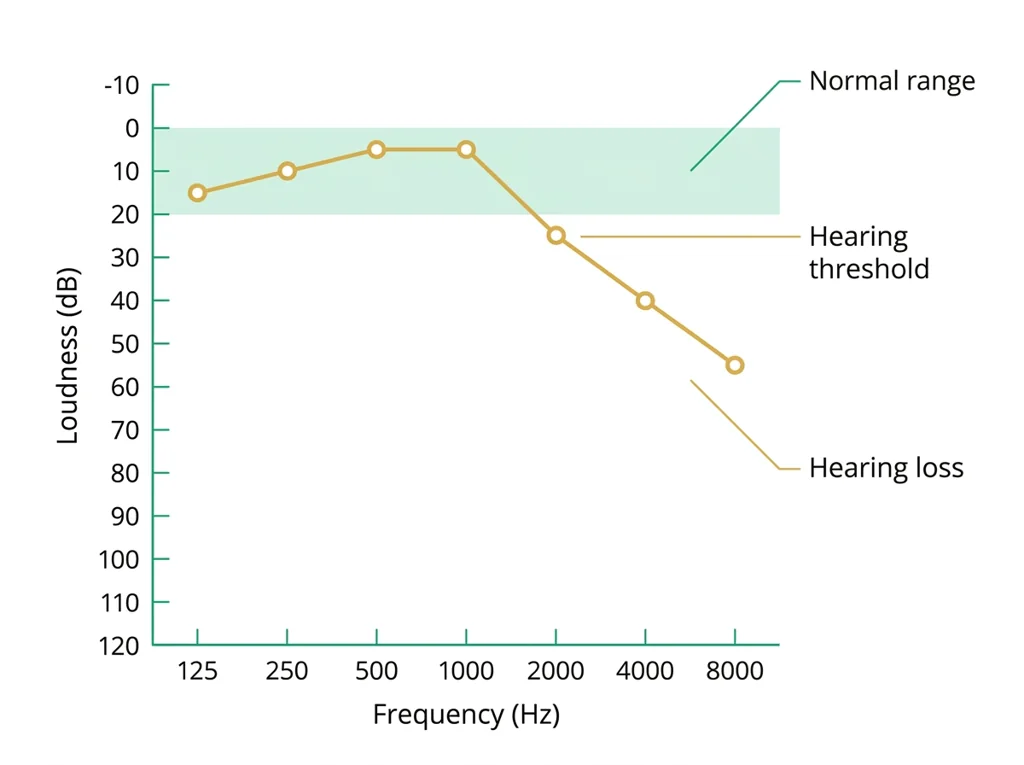
- • : A graph from a hearing test that plots the softest sounds a person can hear at different pitches, showing the type and degree of any hearing loss.
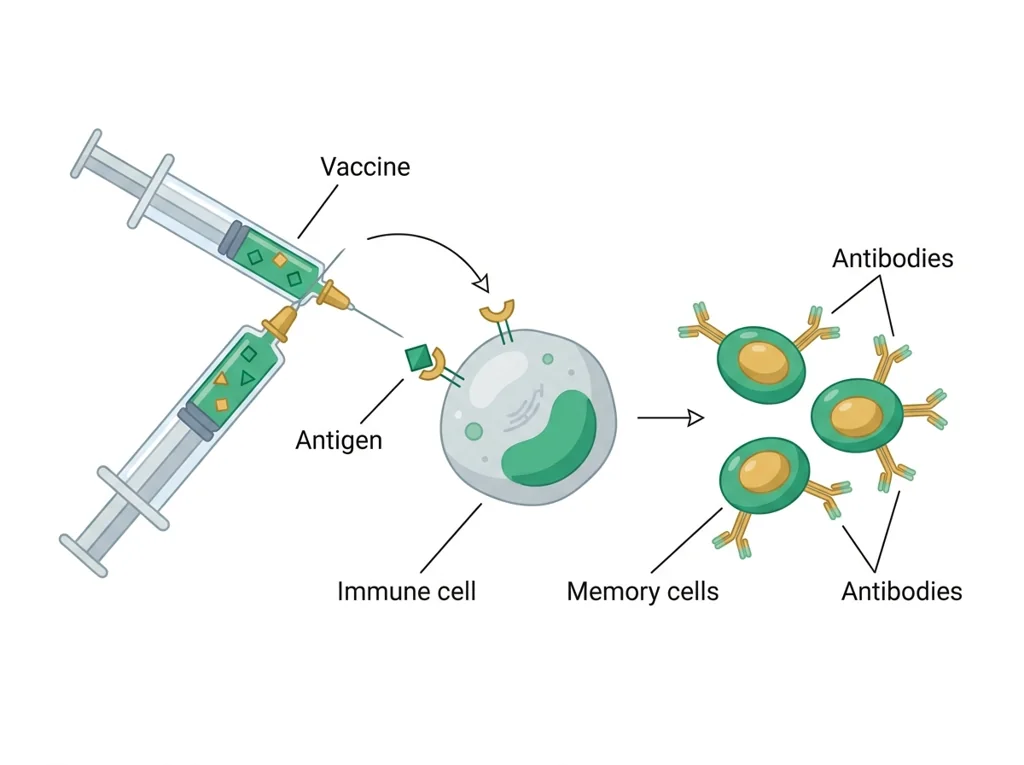
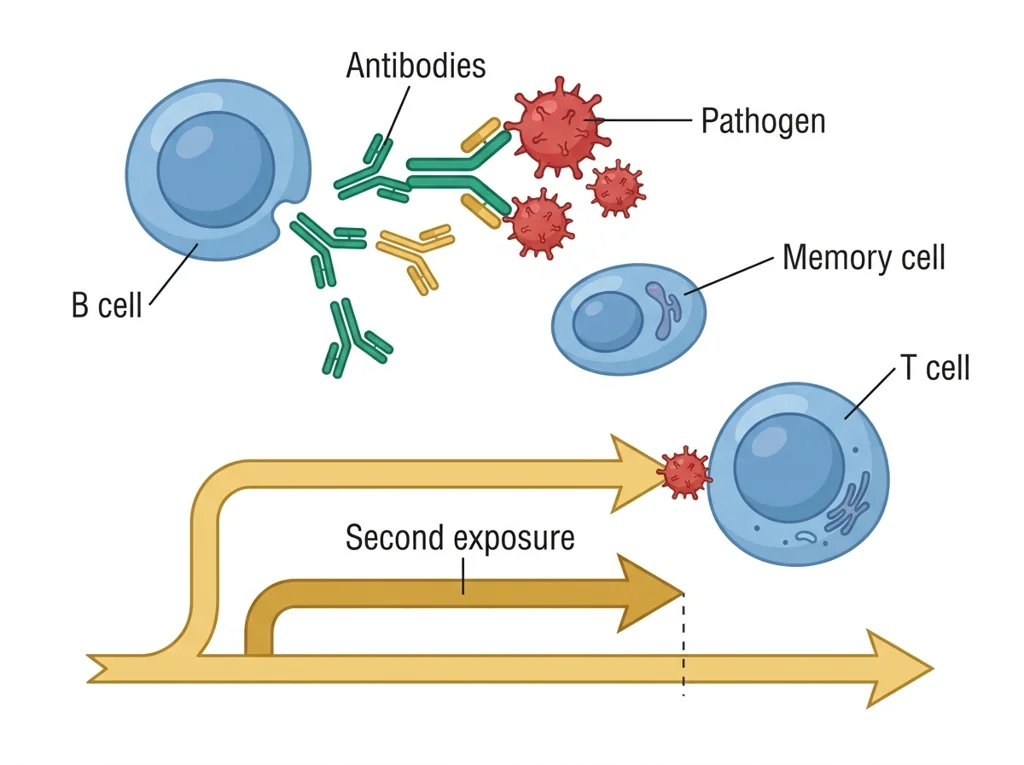
- • : A preparation that delivers an (or the instructions to make one) so the immune system learns to recognize the real later.
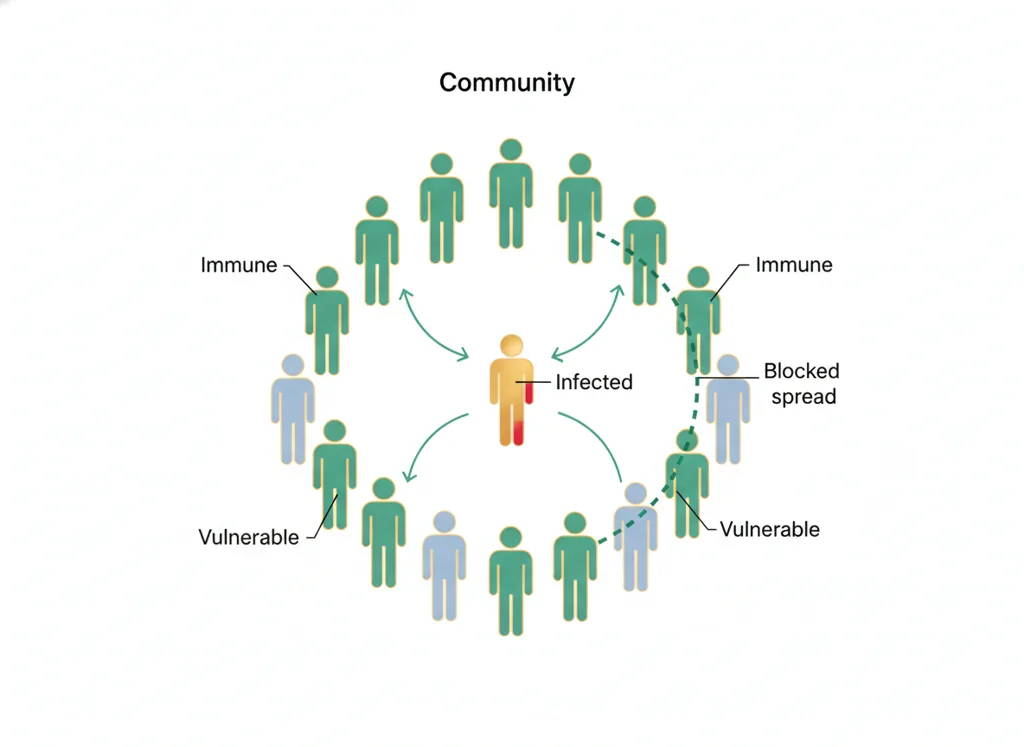
- • : Protection that arises when enough people in a community are immune to a disease that its spread slows and shields those who are not immune.
- • : The part of the immune system that learns a specific , builds targeted antibodies and memory cells, and responds faster the next time it appears.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
An records hearing thresholds by frequency and intensity; it helps characterize hearing loss but does not predict every real-world speech perception outcome by itself.
Limit: Interpretation also depends on test conditions, type of hearing loss, speech testing, history, and clinical evaluation.
A decision is stronger when the test fits the question and its limits are known.
Limit: Medical decisions also depend on biology, patient context, ethics, and professional judgment.
You can plot and read thresholds on an .
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: medical interventions team member
Decision: Your team must decide what the evidence from interpretation supports before submitting the labeled and result claim named on today's page.
- • Test actual speech understanding before saying which everyday sounds this patient misses, since thresholds alone do not predict that.
- • Read a line farther down the chart as worse hearing, because it took a louder sound before the patient responded.
- • Call the line near the top of the chart the worse hearing, since a higher spot means a higher number.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about interpretation. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from interpretation supports before submitting the labeled and result claim named on today's page.
Context: A single well-designed graph can convert a private, invisible experience into a shared measurement that drives real medical decisions.
- • T1: Label the two axes of a blank : frequency in hertz across the top, loudness in decibels down the side.
- • T2: Trace one patient's right-ear and left-ear thresholds onto the chart from the Activity 1.3.2 ; if myPLTW will not open, use this practice set (dB HL at 250, 500, 1000, 2000 and 4000 Hz): right ear 25, 30, 40, 60, 70; left ear 20, 25, 30, 45, 55.
- • T3: Mark the speech banana region and decide which sounds this patient would and would not hear.
- • T4: Set the degree for each ear from the pure-tone average of 500, 1000 and 2000 Hz (add the three, divide by three), name its band, and write one sentence of evidence for your call, noting where the loss is worse by frequency.
- • T5: Submit your labeled and classification as your daily evidence.
- • E1: An records hearing thresholds by frequency and intensity; it helps characterize hearing loss but does not predict every real-world speech perception outcome by itself.
- • E2: A decision is stronger when the test fits the question and its limits are known.
- • E3: You can plot and read thresholds on an .
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Pure-tone average (PTA) = (500 Hz + 1000 Hz + 2000 Hz thresholds) / 3 = (35 + 45 + 55) / 3 = 45 dB HL. On the scale, 41 to 55 is moderate, so this ear has a moderate loss. Where the loss is worse by frequency is described separately.
Right-ear thresholds are 35 dB HL at 500 Hz, 45 at 1000 Hz and 55 at 2000 Hz. What is the pure-tone average, and which band is it in?
The average must sit between the smallest and the largest of the three thresholds. An average below 0 or above 120 dB HL means a copying error.
Compute the PTA for each ear from your plotted data, name each ear's band, then write one sentence on where the loss is worse by frequency.
Students often think the like a normal graph and assume a line near the top of the chart means worse hearing because it is a 'high' number. The trap: On an the threshold axis increases downward, so a line lower on the chart means it took a louder sound before the patient heard it, which is worse hearing. Reading it upside down flips every classification, so a profound loss gets mislabeled as normal.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.
Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Audiogram interpretation. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
Use the materials named in the first step below. Open lesson resources.
2.2 Start the work
Label the two axes of a blank audiogram: frequency in hertz across the top, loudness in decibels down the side.
Show all 5 required steps
- Label the two axes of a blank audiogram: frequency in hertz across the top, loudness in decibels down the side.
- Trace one patient's right-ear and left-ear thresholds onto the chart from the Activity 1.3.2 data table; if myPLTW will not open, use this practice set (dB HL at 250, 500, 1000, 2000 and 4000 Hz): right ear 25, 30, 40, 60, 70; left ear 20, 25, 30, 45, 55.
- Mark the speech banana region and decide which sounds this patient would and would not hear.
- Set the degree for each ear from the pure-tone average of 500, 1000 and 2000 Hz (add the three, divide by three), name its band, and write one sentence of evidence for your call, noting where the loss is worse by frequency.
- Submit your labeled audiogram and classification as your daily evidence.
Lost your place? Your audiogram should already have both axes labeled and both ears traced from the Activity 1.3.2 data table or the practice set in step 2. If it does, your next move is to mark the speech banana, set each ear's degree from its pure-tone average, and write one sentence of evidence before you submit.
- 0-8Axis labeling guided practice on blank
- 8-20Trace right- and left-ear thresholds from
- 20-35Mark speech banana; identify which phonemes patient misses
- 35-50Classify loss severity; write evidence sentence
- 50-70Partner check: swap audiograms, verify each other's plots
- 70-80Submit labeled and classification; preview the and disease-model lab
- • Hook: Show a blank and ask students what they think the axes mean before labeling.
- • Why it matters: Every cochlear implant candidacy decision starts with reading this graph.
- • Today's work: You will plot real threshold data and classify a patient's loss using clinical ranges.
- • Exit goal: Labeled and one-sentence severity classification submitted by block end.
PLTW connection and today's work
Open Activity 1.3.2 Can You Hear Me Now? in myPLTW and use its audiogram data to plot and classify hearing thresholds; if it will not open, use the practice data set in step 2.
Today's stopping point: The debate should be posted; audiogram work due today.
PLTW activity titles identify the course connection. If your account will not open, use the posted materials for today and tell Mr. Mendoza. Do not mark an online activity complete unless you completed it.
Course connection
- Activity 1.3.2 Can You Hear Me Now?
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
I labeled the axes: frequency in hertz across the top (low pitch on the left, high pitch on the right) and loudness in decibels down the side (soft at the top, loud at the bottom). I plotted Patient A's right-ear thresholds from the data table.
What the plot shows: Patient A hears low frequencies at about 30 dB but needs high frequencies (2000 to 4000 Hz) turned up to 55 to 65 dB before hearing them. That high-frequency region overlaps part of the speech banana, so this patient would miss soft consonant sounds like s, f, and th while still hearing vowels.
Classification: I set the degree from the pure-tone average of 500, 1000 and 2000 Hz: (35 + 45 + 55) / 3 = 45 dB HL, which is a moderate hearing loss on the scale. The loss is worse at high frequencies, where 4000 Hz sits at 65 dB HL, in the moderately severe band. So: a moderate, high-frequency sloping loss in the right ear.
Patient A is a practice patient; your patient's thresholds and average will differ.
| Frequency (Hz) | Right-ear threshold (dB HL) |
|---|---|
| 250 | 30 |
| 500 | 35 |
| 1000 | 45 |
| 2000 | 55 |
| 4000 | 65 |
This model shows the level of evidence and organization needed to complete: Completes the audiogram reading task: a labeled audiogram with plotted thresholds, the speech banana marked, and a one-sentence severity classification with evidence.
- Name the variables and include units.
- Enter observations without changing the raw values.
- Check labels, calculations, and patterns before interpreting the data.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Submit your annotated audiogram and classification in Schoology.
An airport checkpoint uses an ID check, a metal detector, and an X-ray scanner.
- What can the ID check detect?
- What might set off the metal detector by mistake?
- Why do we need the X-ray if we already checked their ID?
A decision is stronger when the test fits the question and its limits are known.
Medical decisions also depend on biology, patient context, ethics, and professional judgment.
- • The ID check maps to confirming patient identity.
- • The metal detector maps to a rapid, non-specific screening test.
- • The X-ray scanner maps to a detailed, specific diagnostic test.
Part 4 of 4 · Your work▸
Check your work before submitting
- You'll be able to plot and read thresholds on an audiogram.
- You'll be able to classify a hearing loss by severity from the data.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- Labeled audiogram with both ears plotted, the speech banana marked, the pure-tone average for each ear, and a one-sentence severity classification with its evidence.
How to submit and name your file
Submit the labeled audiogram and the classification sentence as one PDF in Schoology.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Find this lesson's Schoology assignments
These are existing assignments for your section. Follow the directions in the assignment you are working on; this list does not add new work. A PLTW Work row repeats on every day of its lesson; submit it once. Check Schoology for each deadline.
- Wk7 Data table: Audiogram interpretation(today's turn-in)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: A cochlear implant carries a hidden claim about what counts as normal, so deciding to use it on a child who cannot consent is an ethical choice, not just a clinical one. Today: The audiogram plots louder thresholds farther down the chart so that a lower line reads as worse hearing, which lets a clinician classify severity and predict which range of speech sounds is likely to be hardest to hear.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about interpretation. It cannot prove causation, diagnose a real patient, or justify action outside this room.
A patient's right-ear thresholds are 20 dB HL at 500 Hz, 30 at 1000 Hz, 40 at 2000 Hz and 68 at 4000 Hz. Set the degree of the loss and name the evidence for your call.
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
Today is individual work you can do from home: complete the same target above, then submit your Data table.
Go to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
NIH MedlinePlusSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Classroom documents for this lesson are posted in Schoology. Open Clever, then Schoology, and find each one by the name shown on its card.
Use this with the vaccination lesson to connect development to a real example.
Use this if you were absent, got stuck, or need another pass before you submit the lesson artifact.
Use this if you were absent, got stuck, or need another pass before you submit the lesson artifact.
Open this when the class reaches this activity and use it to complete the required lesson artifact.
Sign in to Clever with your district Microsoft account to open Schoology or myPLTW. Follow today's posted steps. If myPLTW will not open, use the posted alternative and tell Mr. Mendoza. Turn in your completed work through the Schoology assignment.
This week
My Progress dashboard