
Treatment recommendation draft
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Draft a treatment plan recommendation that follows from the sorted evidence and named risks.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: Tracing each step of a plan to ranked evidence, and naming what would overturn it, is what separates clinical reasoning from a confident guess.
- • A treatment recommendation has three parts: the diagnosis (what we believe), the plan (what we will do), and monitoring (how we will know if we were wrong).
- • Naming a false-result risk in the plan is not weakness; it is how clinicians build in a net.
- • Every element of the plan should point to a specific piece of evidence; unsupported steps signal guessing, not clinical reasoning.
Should vaccination be mandatory?
Tracing each step of a plan to ranked evidence, and naming what would overturn it, is what separates clinical reasoning from a confident guess.
Driving question: You have sorted the evidence. Now write what you would actually do for the practice patient, and say how you would know if it was the wrong call.
What you already know: From the class before the John Carroll debate: The cost of a wrong result depends on the decision it feeds, so the same error rate is acceptable for screening and unacceptable for a surgical decision.
New idea: Tracing each step of a plan to ranked evidence, and naming what would overturn it, is what separates clinical reasoning from a confident guess.
- Observe or measure the relevant feature in treatment recommendation draft.
- Organize the observation with a stable evidence ID.
- Apply this rule: Keep observations separate from explanations, then collect the evidence that can distinguish the options.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: You have sorted the evidence. Now write what you would actually do for the practice patient, and say how you would know if it was the wrong call.
What the evidence supports: E1 to E3 and the figure support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
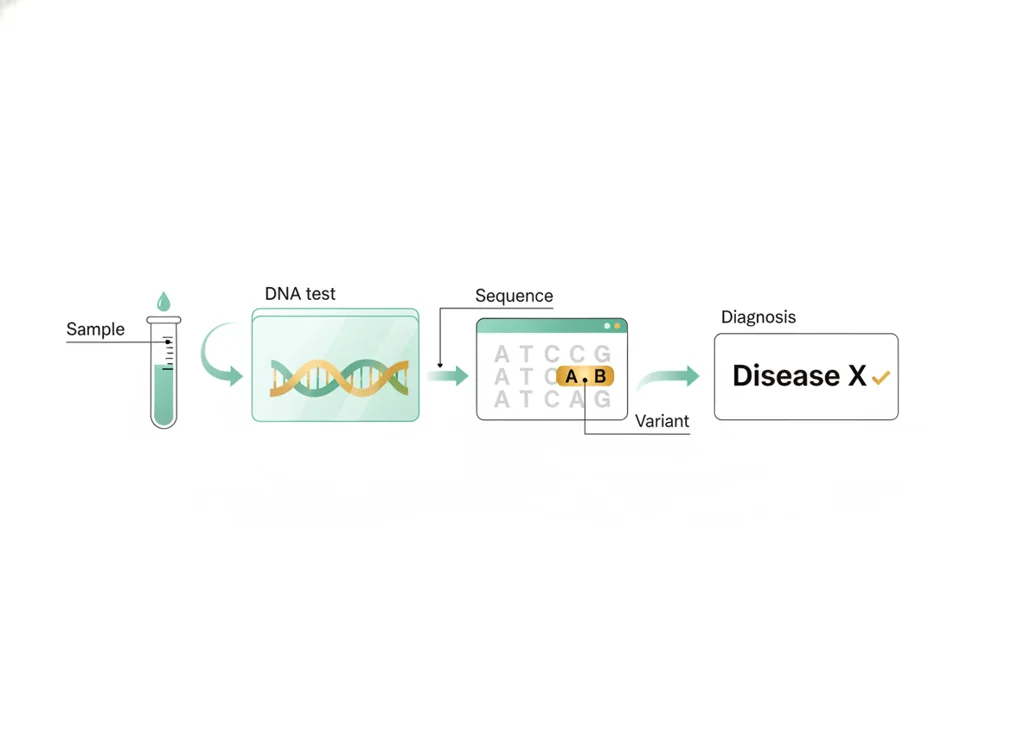
- • : Identifying a disease by detecting specific , RNA, or proteins in a sample, allowing precise diagnosis at the level of genes and molecules.
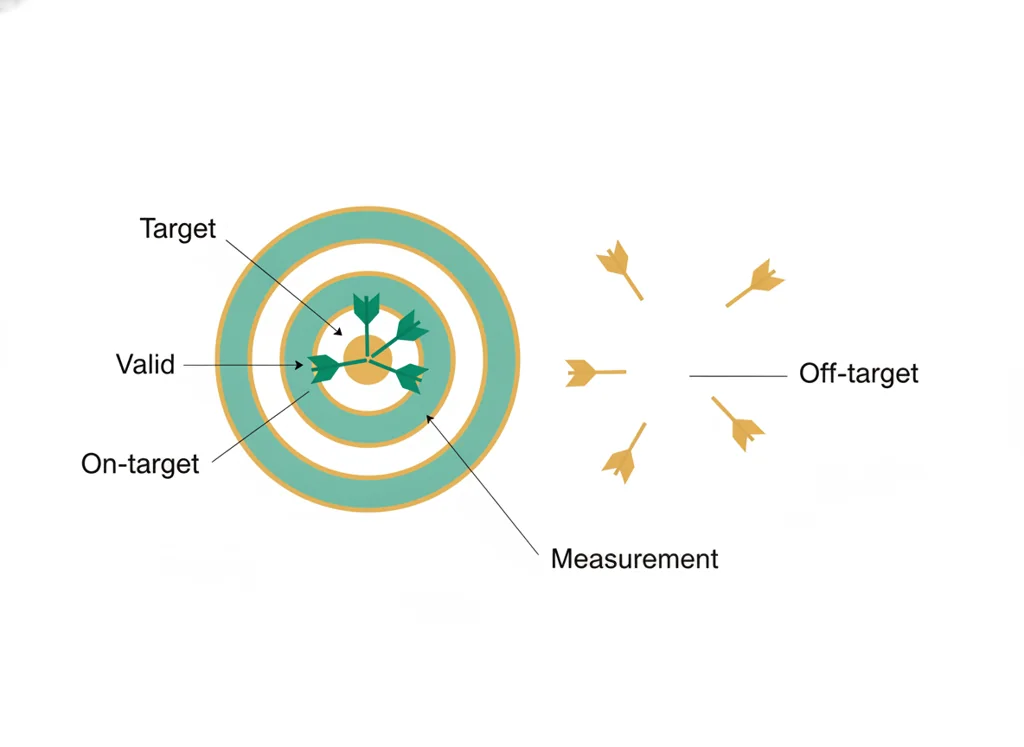
- • validity: How well a test or study actually measures what it claims to, so the conclusions truly reflect reality.
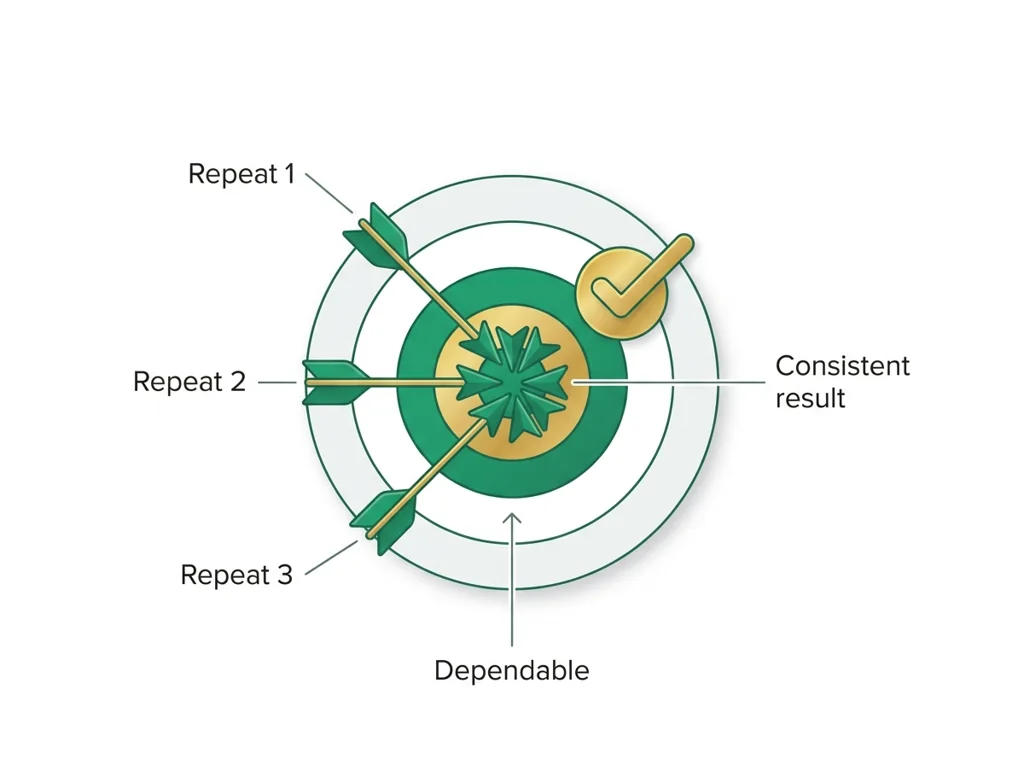
- • reliability: The degree to which a measurement, method, or person produces the same dependable result each time under the same conditions.
- • : A test result that signals a condition is present when it actually is not, a kind of error that can lead to needless worry or treatment.
- • : A test result that says a condition is absent when it is actually present, missing a true case.
- • : An organized roadmap of the steps, therapies, and goals a healthcare team will follow to manage or cure a patient's condition.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
A classroom clinical recommendation must connect case findings to a plausible mechanism, expected benefit and harm, alternatives, and uncertainty without presenting the composite case as a real diagnosis or prescription.
Limit: The classroom case omits clinical history, examination, validated testing, patient preferences, and professional judgment needed for real care.
Keep observations separate from explanations, then collect the evidence that can distinguish the options.
Limit: Biomedical investigations use controlled procedures and validated measurements, not intuition alone.
You can build a from sorted evidence.
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: medical interventions team member
Decision: Your team must decide what the evidence from treatment recommendation draft supports before submitting the claim-evidence-reasoning response named on today's page.
- • Hold the plan as a draft until you have the clinical history, exam, and validated testing the case omits.
- • Write the plan with the mechanism, the expected benefit and harm, one alternative, and the leftover uncertainty.
- • Submit the version that reads most like a real doctor's note, since a polished plan is a convincing plan.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about treatment recommendation draft. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from treatment recommendation draft supports before submitting the claim-evidence-reasoning response named on today's page.
Context: A plan is defensible when every step traces to a named piece of evidence and the plan says in advance how it would detect that it was wrong.
- • T1: Review the evidence sort you made from the practice test history (the Nov 10 page) and choose the strongest results to base a plan on.
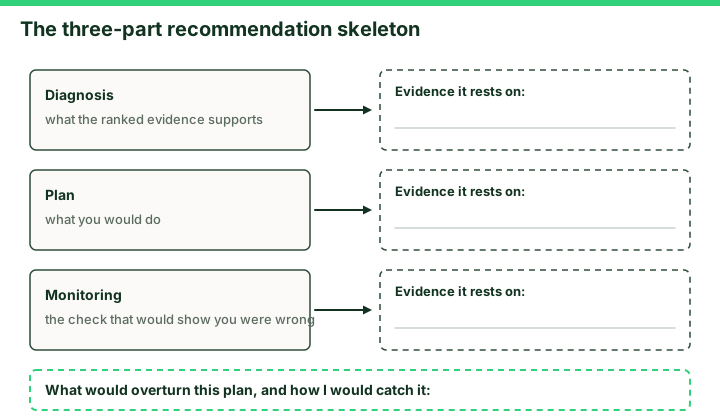
- • T2: Draft a treatment recommendation for the practice patient using this three-part skeleton: Diagnosis (what the ranked evidence supports), Plan (what you would do), Monitoring (the check that would show you were wrong).
- • T3: State one false-result risk that could change the plan and how you would catch it.
- • T4: Check that each part of the plan traces to a piece of evidence.
- • T5: Submit your treatment recommendation draft as your daily evidence.
- • E1: A classroom clinical recommendation must connect case findings to a plausible mechanism, expected benefit and harm, alternatives, and uncertainty without presenting the composite case as a real diagnosis or prescription.
- • E2: Keep observations separate from explanations, then collect the evidence that can distinguish the options.
- • E3: You can build a from sorted evidence.
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Figure finding: Three stacked boxes labeled Diagnosis, Plan and Monitoring, each with a short description and an arrow to an empty dashed slot titled Evidence it rests on, and a dashed strip at the bottom for what would overturn this plan and how I would catch it.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Students often think a strong recommendation is one stated with the most certainty. The trap: Unhedged certainty is what makes a plan undefendable, because it gives no trigger to revisit the decision. The monitoring step is the part that makes the plan safe, and leaving it out to sound decisive is the trap.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.
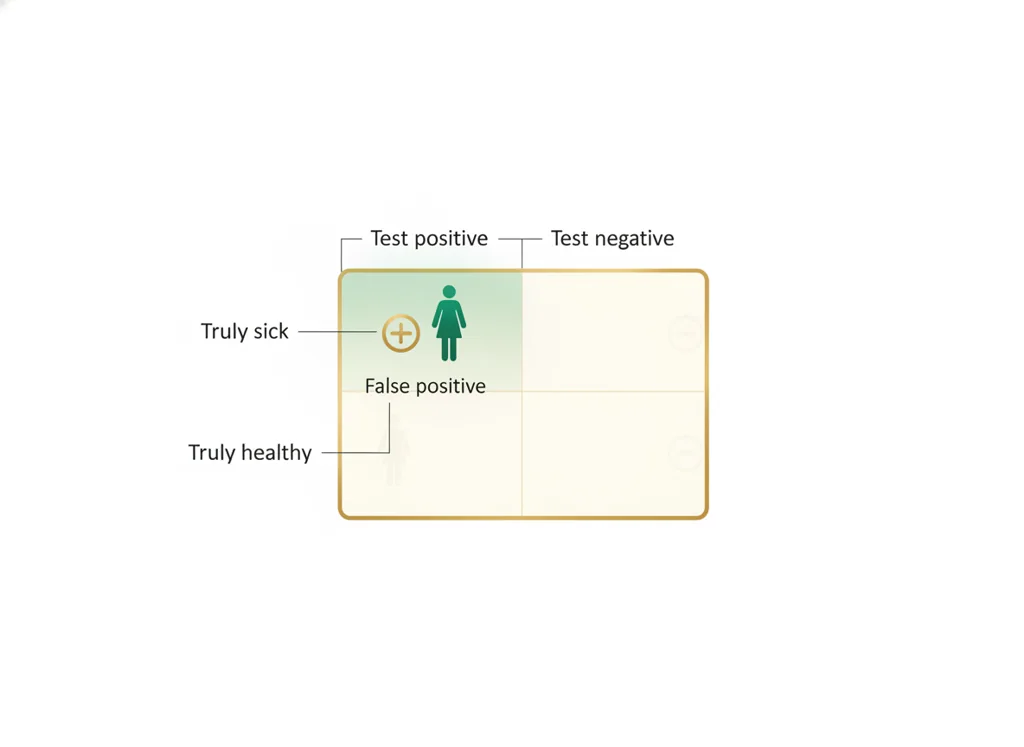
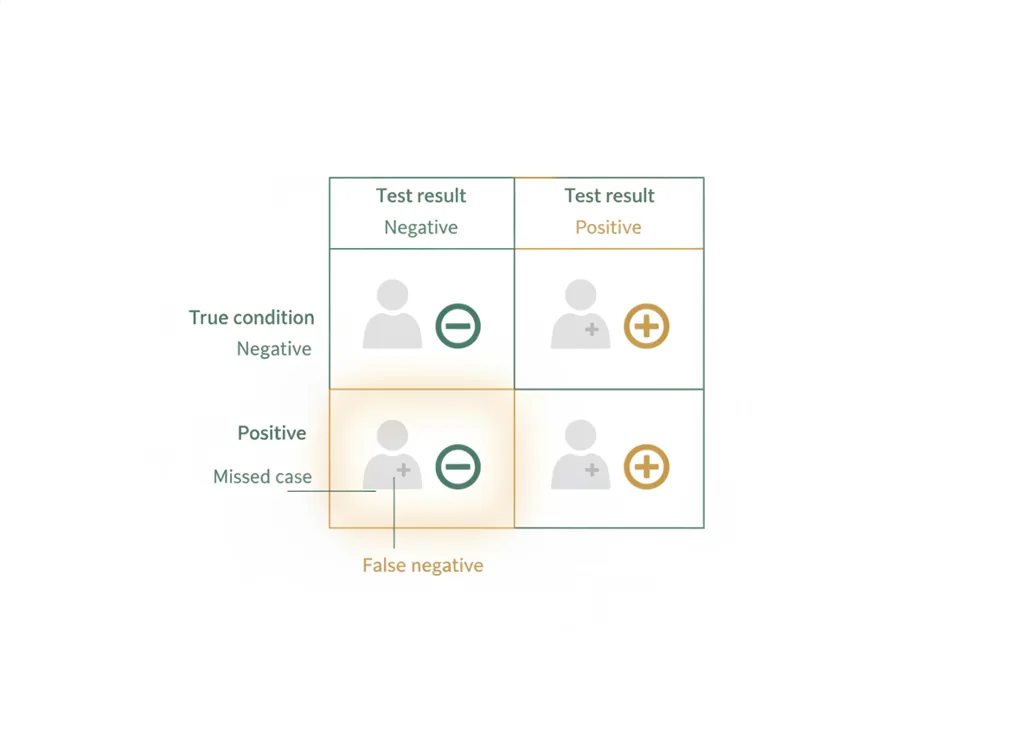
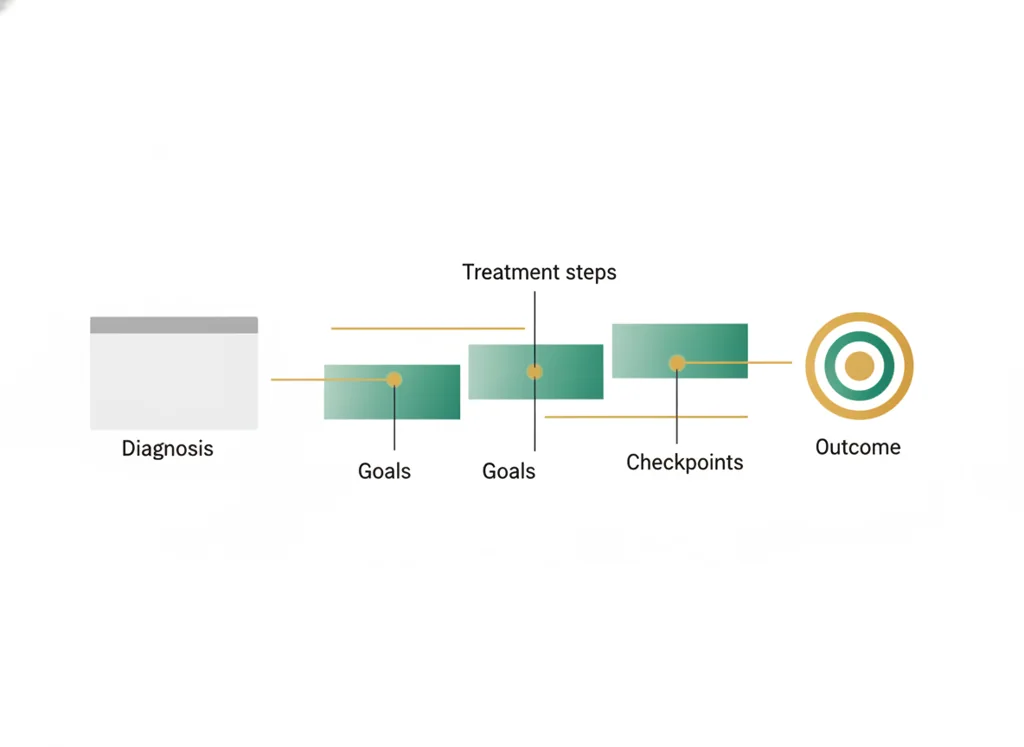
Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Treatment recommendation draft. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
Use the materials named in the first step below. Open lesson resources.
2.2 Start the work
Review the evidence sort you made from the practice test history (the Nov 10 page) and choose the strongest results to base a plan on.
Show all 5 required steps
- Review the evidence sort you made from the practice test history (the Nov 10 page) and choose the strongest results to base a plan on.
- Draft a treatment recommendation for the practice patient using this three-part skeleton: Diagnosis (what the ranked evidence supports), Plan (what you would do), Monitoring (the check that would show you were wrong).
- State one false-result risk that could change the plan and how you would catch it.
- Check that each part of the plan traces to a piece of evidence.
- Submit your treatment recommendation draft as your daily evidence.
Lost your place? Your plan needs three labelled parts. Write the diagnosis line first, then the plan, then the one monitoring step, and check each traces to a result.
- 0-8Hook clinical note; identify the three-part structure
- 8-20Review evidence sort; select two strongest results for the plan foundation
- 20-50Draft treatment recommendation: diagnosis, plan, one monitoring step
- 50-62State one false-result risk and how you would catch it
- 62-72Self-check: trace each plan element back to a specific evidence item
- 72-80Submit treatment recommendation draft; preview Unit 3, which opens next class
- • Hook: Show a one-page clinical summary note and ask: what are the three things every must answer?
- • Why it matters: Writing a data-anchored is the culminating skill of the Genetics of Disease course.
- • Today's work: You draft the plan for the practice patient from your evidence sort; Unit 3 opens next class with cell microscopy.
- • Exit goal: Treatment recommendation draft with evidence links and one statement submitted before the bell.
PLTW connection and today's work
Open Activity 2.2.2 Reproductive Technology in myPLTW for the background, then draft a treatment recommendation for the practice patient from your sorted evidence.
Today's stopping point: Evidence sort should be done; treatment recommendation draft due today.
PLTW activity titles identify the course connection. If your account will not open, use the posted materials for today and tell Mr. Mendoza. Do not mark an online activity complete unless you completed it.
Course connection
- Activity 2.2.2 Reproductive Technology
The mapping has not been confirmed inside myPLTW.
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
Parallel case, not today's patient: an adult reports months of fatigue, cold intolerance, and weight gain. TSH is high and free T4 is low on two separate draws.
Diagnosis: primary hypothyroidism.
Evidence it rests on: a raised TSH together with a low free T4, on two separate draws. The second draw is doing real work here, because a single abnormal thyroid panel can reflect a passing illness rather than the thyroid itself.
Plan: start levothyroxine at a weight-based dose, taken on an empty stomach and separated from calcium and iron.
Evidence it rests on: the hormone that is missing is thyroxine, so replacing thyroxine treats the cause rather than the symptoms, and absorption is the main thing that makes a correct dose behave like a wrong one.
Monitoring step: recheck TSH in six to eight weeks, and again after any dose change.
Why this step is in the plan: it is the part that could tell me I was wrong. TSH moves slowly, so six to eight weeks is roughly how long it takes to settle at a new dose, and testing sooner reads noise as if it were signal.
False-result risk I am guarding against: interference inside the thyroid immunoassay itself. Heterophile antibodies in a patient's blood can bind the assay reagents and push a TSH reading up with no thyroid disease behind it, and a panel drawn while the body is recovering from another illness can look abnormal for a few weeks. (High-dose biotin is a different trap: on many assays it pushes TSH down and free T4 up, so it fakes an overactive thyroid, not this pattern.)
How I would catch it: ask about recent illness and supplements, repeat the panel after recovery, and if the numbers still disagree with the clinical picture, ask the lab to rerun TSH on a different assay platform before acting.
What would overturn this plan: a repeat TSH in the normal range on a second method, which would mean the first results were the assay and not the patient.
How to use this: today's patient is not this one. Build your recommendation the same way. Name the diagnosis, name the plan, name the check that could prove you wrong, and point every part of it at a specific result.
This model shows the level of evidence and organization needed to complete: A treatment recommendation for a DIFFERENT patient from today's, modeling the exact structure students must produce, diagnosis, plan, monitoring step, and a named false-result risk with how it would be caught, without answering today's own case.
- Write one defensible claim.
- Choose specific evidence that supports the claim.
- Explain the scientific rule that connects the evidence to the claim.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Submit the treatment recommendation draft in Schoology by end of period.
A detective board holds observations, possible explanations, and one next question.
- Which notes are direct observations?
- Which notes are explanations?
- What new evidence would separate the explanations?
Keep observations separate from explanations, then collect the evidence that can distinguish the options.
Biomedical investigations use controlled procedures and validated measurements, not intuition alone.
- • Board notes map to the signs, results and measurements you recorded.
- • Possible explanations map to the competing biological causes.
- • The next question maps to the test or observation that would separate them.
Part 4 of 4 · Your work▸
Check your work before submitting
- You'll be able to build a treatment plan from sorted evidence.
- You'll be able to name and guard against a false-result risk.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- Treatment recommendation draft: diagnosis, plan, one monitoring step, one named false-result risk with detection strategy, each element linked to evidence.
How to submit and name your file
Submit as one PDF in Schoology.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Today's lesson is in Schoology
Each school day has one lesson page in Schoology that holds everything for the day: the goal, the story so far, every table and data value, the numbered steps, and what to turn in. Open it first and work from it. The other rows for this day, if any, are the score line for a paper quiz or test and the John Carroll debate item; they do not add work. Check Schoology for each deadline.
- Today's Lesson · Fri 11/13 · Wk12 · Four lung cancer patients and their microarray cards, then pick the genes to study(today's lesson page: the goal, the data, the steps, and what to turn in are all on it)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: Should vaccination be mandatory? Today: Tracing each step of a plan to ranked evidence, and naming what would overturn it, is what separates clinical reasoning from a confident guess.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about treatment recommendation draft. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Your plan rests on one result that could be a false positive. What belongs in the monitoring step?
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
Today is individual work you can do from home: complete the same target above, then submit your CER.
Go to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
MedlinePlus: How is genetic testing done and what do results mean?The optional extra-credit track is open. Complete reserved-unit work from home, including virtual labs, for extra credit. Each item shows its correct submission route.
Open the extra-credit trackSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Classroom documents for this lesson are posted in Schoology. Open Clever, then Schoology, and find each one by the name shown on its card.
Use this if you were absent, got stuck, or need another pass before you submit the lesson artifact.
Use this after the required lesson work when you are ready for a harder application or a deeper connection.
Use this after the required lesson work when you are ready for a harder application or a deeper connection.
Sign in to Clever with your district Microsoft account to open Schoology or myPLTW. Follow today's posted steps. If myPLTW will not open, use the posted alternative and tell Mr. Mendoza. Turn in your completed work through the Schoology assignment.
This week
My Progress dashboard