
Diagnostic disclosure debate
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Students debate how much diagnostic uncertainty a clinician should share with a new patient.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: requires disclosing uncertainty, not just facts, because a patient cannot truly agree to a plan whose real risks and unknowns were hidden from them.
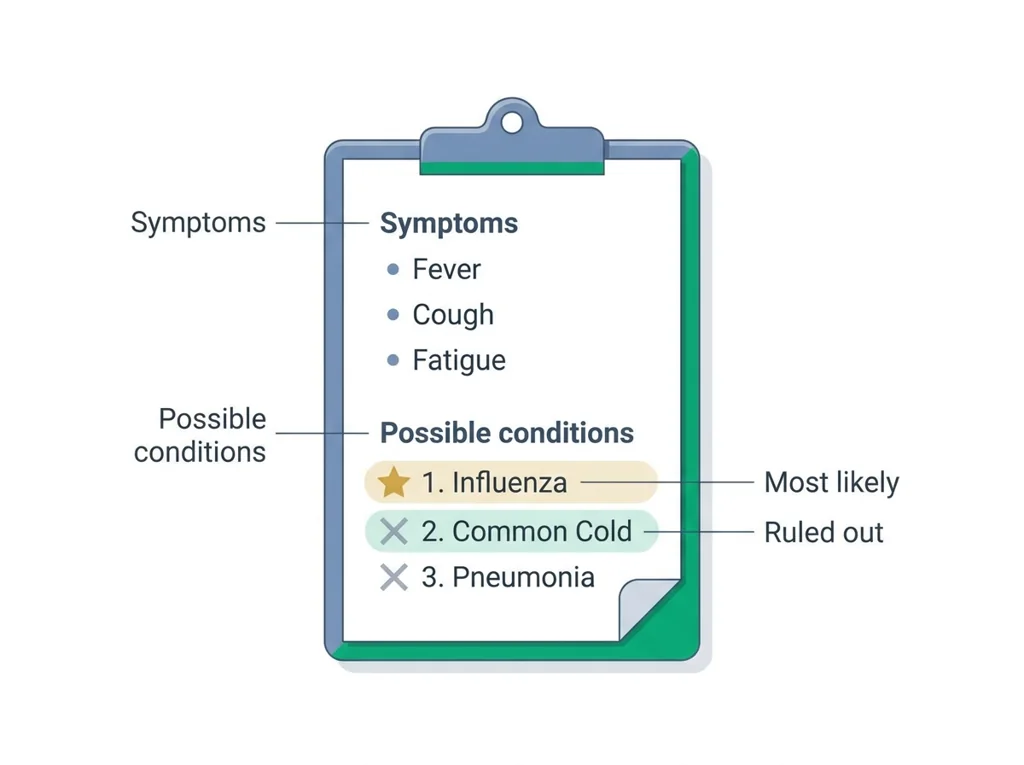
- • is an ordered list of possible conditions ranked by likelihood.
- • Shared decision-making balances clinical expertise with the patient's right to understand their own data.
- • Full versus staged disclosure each carry distinct patient-centered and clinical tradeoffs.
Should children reach the age of consent before cochlear implants or other medical interventions are allowed?
requires disclosing uncertainty, not just facts, because a patient cannot truly agree to a plan whose real risks and unknowns were hidden from them.
Driving question: A new patient's early test results are ambiguous and could point to two very different conditions. Do you tell them everything now, or wait until the picture is clearer?
New idea: requires disclosing uncertainty, not just facts, because a patient cannot truly agree to a plan whose real risks and unknowns were hidden from them.
Visual or model: No figure is attached to this lesson. The readings, the worked example and E1 to E3 carry the evidence.
- Observe or measure the relevant feature in diagnostic disclosure debate.
- Organize the observation with a stable evidence ID.
- Apply this rule: Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: A new patient's early test results are ambiguous and could point to two very different conditions. Do you tell them everything now, or wait until the picture is clearer?
What the evidence supports: E1 to E3 support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
- • : The ranked list of conditions that could explain a patient's story. The whole game is narrowing it honestly.
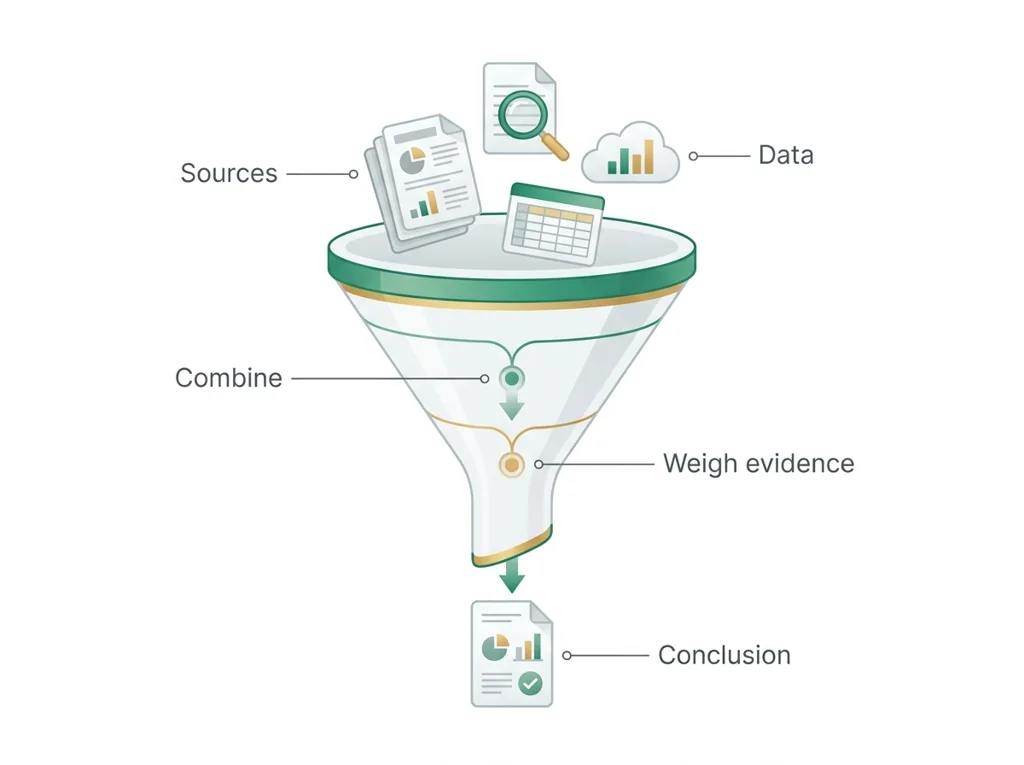
- • : Combining findings from many separate sources into one organized conclusion, weighing how strong and consistent the evidence is overall.
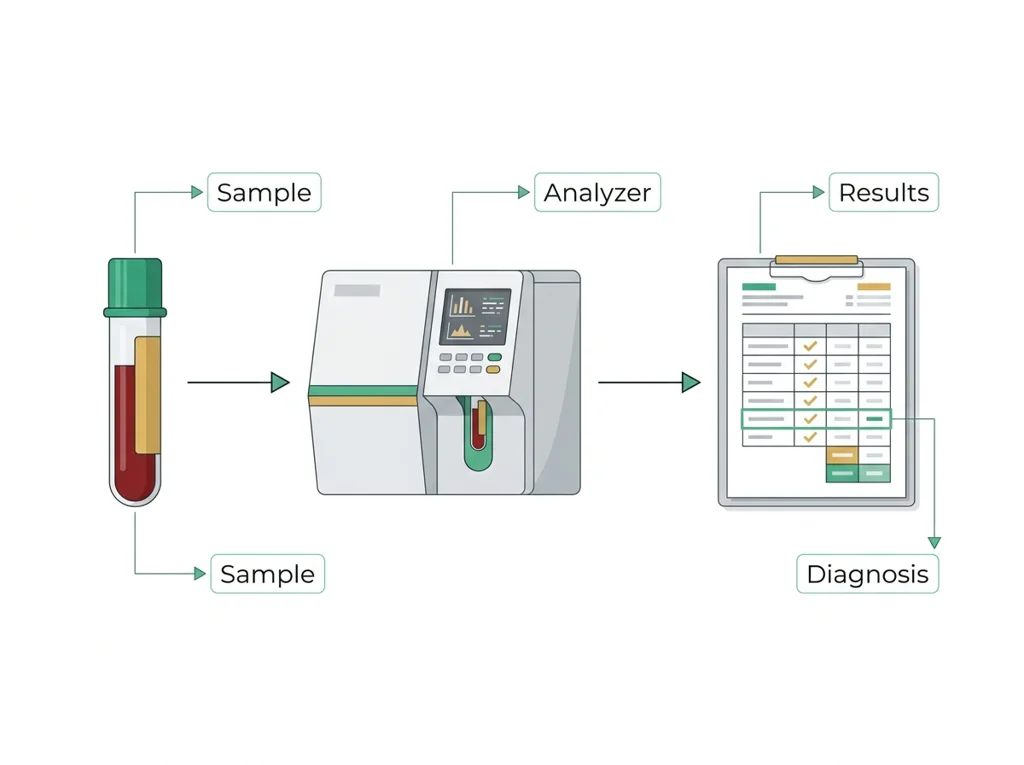
- • : A procedure that analyzes a sample of blood, urine, or to provide measurable information that helps diagnose or monitor a condition.
- • : An organized record of a patient's medical history, test results, medications, and care, used by the healthcare team to make decisions.
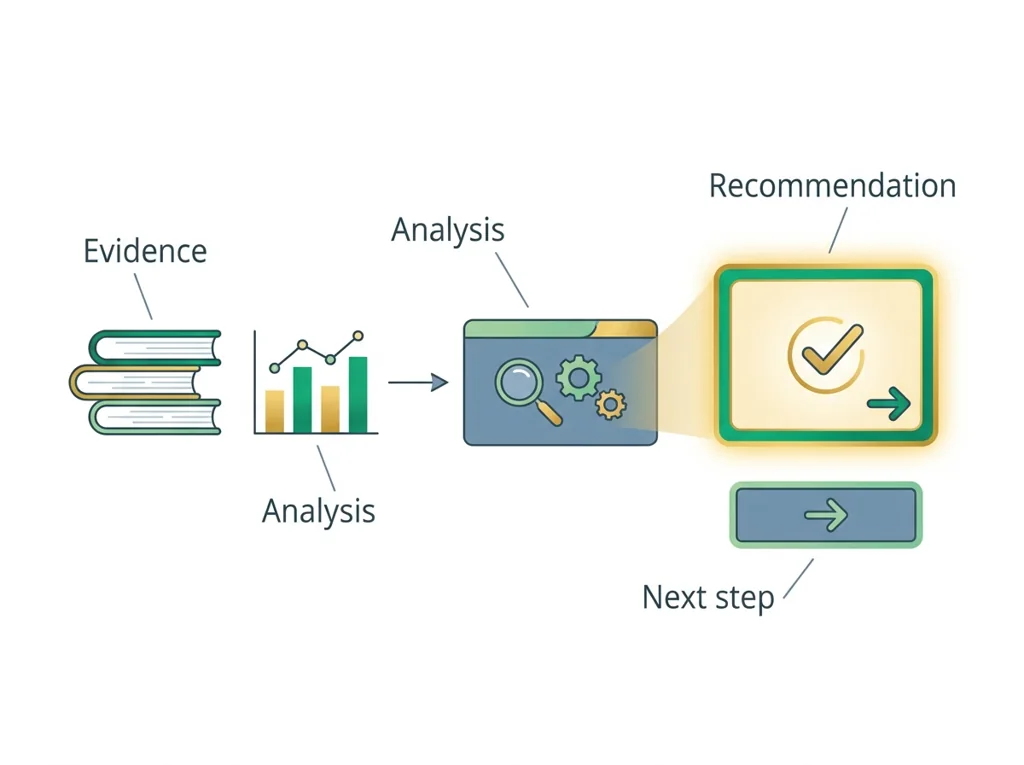
- • recommendation: A clear, evidence-based suggestion for what action to take, drawn from analyzing data, results, or a patient's situation.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
A defensible biomedical decision separates scientific evidence from value judgments, identifies who may benefit or be burdened, and states the uncertainty and tradeoffs that remain.
Limit: Scientific evidence can inform the options and likely consequences, but it cannot choose a single value-neutral answer.
Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
Limit: A review-board model organizes reasoning but does not make one ethical principle automatically outweigh every other principle.
Defend a position with patient-centered and clinical evidence.
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: biomedical team member
Decision: Your team must decide what the evidence from diagnostic disclosure debate supports before submitting the exit response named on today's page.
- • Tell the patient what is known and how sure you are, since consent needs the uncertainty named, not every possible condition.
- • Read the whole differential aloud at the first abnormal result, because full honesty means the patient hears every possibility.
- • Wait for the confirmatory result before ranking the two conditions aloud, since the early tests cannot yet separate them.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about diagnostic disclosure debate. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from diagnostic disclosure debate supports before submitting the exit response named on today's page.
Context: is a conversation about uncertainty, not a signature on a form, because a patient can only truly agree to a plan they understand.
- • T1: Read this practice case: a new patient's first blood panel shows one value slightly out of range and one borderline, and the clinician holds a ranked list of six possibilities, most of them unlikely. Decide how much of that list the patient should hear today.
- • T2: Choose a stance on full disclosure versus staged disclosure of uncertainty.
- • T3: List two patient-centered and two clinical reasons supporting your stance.
- • T4: Debate using terms like , , and shared decision-making.
- • T5: Summarize the most persuasive counterpoint in one sentence.
- • E1: A defensible biomedical decision separates scientific evidence from value judgments, identifies who may benefit or be burdened, and states the uncertainty and tradeoffs that remain.
- • E2: Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
- • E3: Defend a position with patient-centered and clinical evidence.
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Students often think full honesty always means telling the patient every possible diagnosis the moment a result looks abnormal. The trap: a differential is a ranked list of guesses, not a verdict, so dumping every low-probability condition on a patient can cause real harm (panic, unneeded tests) without adding real information. Honest disclosure means sharing what is known and how sure you are, not reciting every worst case.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.

Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Diagnostic disclosure debate. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
2.2 Start the work
Read this practice case: a new patient's first blood panel shows one value slightly out of range and one borderline, and the clinician holds a ranked list of six possibilities, most of them unlikely. Decide how much of that list the patient should hear today.
Show all 5 required steps
- Read this practice case: a new patient's first blood panel shows one value slightly out of range and one borderline, and the clinician holds a ranked list of six possibilities, most of them unlikely. Decide how much of that list the patient should hear today.
- Choose a stance on full disclosure versus staged disclosure of uncertainty.
- List two patient-centered and two clinical reasons supporting your stance.
- Debate using terms like differential diagnosis, informed consent, and shared decision-making.
- Summarize the most persuasive counterpoint in one sentence.
Lost your place? Reread the practice case in step 1, then pick your stance (full versus staged disclosure) and start listing your two patient-centered and two clinical reasons.
- 0-8 minRead the practice case in step 1; annotate what you would want to know if you were the patient.
- 8-18 minDefine , , shared decision-making.
- 18-35 minBuild two-point argument for your assigned disclosure position.
- 35-60 minStructured debate: full-disclosure vs. staged-disclosure teams, teacher facilitates.
- 60-72 minWrite one-sentence summary of the most persuasive counterpoint.
- 72-80 minWhole-class debrief; preview the team project next class.
- • Doctors make hundreds of disclosure decisions every day, and there is no universal rulebook.
- • Today you practice reasoning through those decisions using real vocabulary from clinical medicine.
- • your end-of-course WebXam tests lab practice; connecting a lab result to what you tell a patient is the professional skill this lesson adds on top of it.
- • The counterpoint you identify at the end is often where the most important clinical thinking lives.
PLTW connection and today's work
Lesson 2.3 New to the Practice in myPLTW opens with Problem 2.3.1 A New Patient; read its opening page if myPLTW opens. Today's debate is a John Hay original.
Today's stopping point: You finished Lesson 2.2. Today starts Lesson 2.3 New to the Practice, which focuses on the full diagnostic workup of a new patient. Nothing is submitted in myPLTW today.
Today uses John Hay teacher-created practice. It builds skills for the course, but does not count as completing an official myPLTW activity.
Course connection
- Problem 2.3.1 A New Patient
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
Parallel case (not today's prompt): A clinician orders an abdominal CT scan to check for kidney stones. The stones are ruled out, but the scan happens to reveal a small, harmless-looking spot on the patient's liver that was not what anyone was looking for. This is called an incidental finding. Should the clinician tell the patient about the unrelated spot, or leave it out of the report because it was not the reason for the scan?
Claim: The clinician should disclose the incidental liver finding to the patient rather than leave it unmentioned.
Evidence: Radiology guidelines classify many incidental findings on a scale from benign to concerning, and a spot that looks harmless can still fall into a category that professional guidelines recommend tracking with a short follow-up scan. The finding is now part of the patient's medical record, which the patient has a legal right to access. In addition, a later, unrelated appointment could surface the same spot with no context, which tends to alarm patients more than a calm explanation given up front.
Reasoning: The evidence supports disclosure because the principle of informed consent means a patient is entitled to material facts about their own body, and a documented finding with a recommended follow-up is material even when it is probably benign. Withholding it would trade the patient's autonomy for the clinician's convenience, while disclosing it respects shared decision-making: the clinician explains what the finding likely is, names the small chance it is something more, and lets the patient help decide whether to do the low-cost follow-up scan. Framed that way, honesty and patient partnership outweigh the mild worry a benign spot might cause.
Counterpoint, one sentence (the exit-ticket format): The most persuasive point against disclosing was that naming a harmless-looking spot can start a chain of scans and worry that the finding never justified.
(Vocabulary used: incidental finding, informed consent, shared decision-making.)
This model shows the level of evidence and organization needed to complete: A worked CER on a parallel case (an incidental finding) that ends with the one-sentence summary of the most persuasive counterpoint the day's exit ticket asks for; it models the format without answering today's disclosure prompt.
- Name the prompt or task.
- Answer it directly with the key evidence.
- Check that the response matches the requested format.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Submit your exit ticket as one PDF to Schoology assignment for this lesson in Schoology. That is the only turn-in today.
A review board sorts scientific evidence, stakeholder needs, possible benefits, possible burdens, and uncertainty before choosing a policy.
- Which statements are scientific evidence?
- Which statements express a value or priority?
- Who receives the benefit and who carries the burden?
Use science to estimate consequences, then state the value judgment and tradeoff that determine the decision.
A review-board model organizes reasoning but does not make one ethical principle automatically outweigh every other principle.
- • Evidence cards map to source-backed findings.
- • Stakeholder cards map to affected people and priorities.
- • The recommendation maps to an explicit tradeoff with a named uncertainty.
Part 4 of 4 · Your work▸
Check your work before submitting
- Defend a position with patient-centered and clinical evidence.
- Use diagnostic vocabulary correctly during the debate.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- One-sentence written summary of the most persuasive counterpoint from the disclosure debate.
How to submit and name your file
Submit your exit ticket as one PDF to the Schoology assignment for this lesson in Schoology. That is the only turn-in today.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Today's lesson is in Schoology
Each school day has one lesson page in Schoology that holds everything for the day: the goal, the story so far, every table and data value, the numbered steps, and what to turn in. Open it first and work from it. The other rows for this day, if any, are the score line for a paper quiz or test and the John Carroll debate item; they do not add work. Check Schoology for each deadline.
- Today's Lesson · Wed 11/4 · Wk11 · Kai's biopsy and diagnosis, then genetic disorders and the jobs of proteins(today's lesson page: the goal, the data, the steps, and what to turn in are all on it)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: Should children reach the age of consent before cochlear implants or other medical interventions are allowed? Today: Informed consent requires disclosing uncertainty, not just facts, because a patient cannot truly agree to a plan whose real risks and unknowns were hidden from them.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about diagnostic disclosure debate. It cannot prove causation, diagnose a real patient, or justify action outside this room.
A patient's screening result is abnormal, but it fits three possible conditions and the clinician is not yet sure which. What is the most defensible thing to disclose right now?
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
At home: read the practice case in step 1, write two patient-centered and two clinical reasons for one stance (full or staged disclosure), and the one-sentence summary of the strongest counterpoint you can think of.
MedlinePlus: Talking With Your DoctorSubmit your exit ticket as one PDF to the Schoology assignment for this lesson in Schoology. That is the only turn-in today.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
NIH MedlinePlus Lab TestsSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Hand-picked readings and interactives for this lesson, from authoritative open organizations and PLTW's own public course outline.
This week
My Progress dashboard