
Response analysis CER
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Students write a CER evaluating their triage and stabilization decisions against patient outcomes.
Check you have the right sheet: the top of it prints today's portal day, Response analysis CER. The PLTW activity itself is in myPLTW and is not posted here.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: You evaluate a decision against the logged evidence and the information you had, not against the final outcome, because outcomes depend partly on severity and chance, so only the evidence-based review reliably points to the next protocol improvement.
- • A CER evaluating uses the decision log as data: specific patient tags and timing are the evidence.
- • A protocol improvement recommendation must be specific and tied to a decision that did not go as planned.
- • Simulation limitations affect the generalizability of conclusions: name at least one that could change the outcome in a real event.
Teams that follow a shared with fixed roles tag and stabilize more patients under pressure, because assigned scope and a repeatable order prevent the missed assessments and duplicated effort that improvising produces.
You evaluate a decision against the logged evidence and the information you had, not against the final outcome, because outcomes depend partly on severity and chance, so only the evidence-based review reliably points to the next protocol improvement.
Driving question: Your decision log shows you tagged one patient yellow who later crashed. Was your order actually the best call given what you knew at the time, and what one change would you make so it does not happen again?
What you already know: Teams that follow a shared with fixed roles tag and stabilize more patients under pressure, because assigned scope and a repeatable order prevent the missed assessments and duplicated effort that improvising produces.
New idea: You evaluate a decision against the logged evidence and the information you had, not against the final outcome, because outcomes depend partly on severity and chance, so only the evidence-based review reliably points to the next protocol improvement.
Visual or model: No figure is attached to this lesson. The readings, the worked example and E1 to E3 carry the evidence.
- Observe or measure the relevant feature in response analysis CER.
- Organize the observation with a stable evidence ID.
- Apply this rule: Define variables, controls, sampling, units, and the analysis plan before interpreting a result; analysis cannot repair biased or inconsistent measurement.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: Your decision log shows you tagged one patient yellow who later crashed. Was your order actually the best call given what you knew at the time, and what one change would you make so it does not happen again?
What the evidence supports: E1 to E3 support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
- • : Sorting patients so that limited staff, time, and supplies do the most good. In everyday emergency care that usually means the most urgent first, but in a mass-casualty event it means treating those who benefit most, which is not always the most badly injured.
- • : The emergency care that keeps a patient's vital functions steady, such as breathing and circulation, so their condition does not worsen before further treatment.
- • : Heavy or uncontrolled bleeding from a damaged blood vessel, either outside the body or internally into tissues, that can become life-threatening.
- • : All the chemical reactions in the body that build up or break down molecules, releasing or storing the energy needed to stay alive.
- • dose: The measured amount of a drug or substance given at one time, chosen to be effective while staying safe for the patient.
- • protocol: A detailed, step-by-step set of instructions for carrying out a procedure the same way every time so results can be trusted and repeated.
- • : A sudden rise in patients that strains a healthcare system beyond normal capacity, as during a disaster, outbreak, or mass-casualty event.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
Biomedical evidence supports a conclusion only to the level allowed by the measurement, comparison, controls, source quality, and uncertainty in the investigation.
Limit: The classroom evidence supports the stated learning decision, not a real clinical diagnosis, causal conclusion, or treatment recommendation.
Define variables, controls, sampling, units, and the analysis plan before interpreting a result; analysis cannot repair biased or inconsistent measurement.
Limit: A well-organized classroom study can still be limited by , measurement quality, confounding, and the population represented.
Write a CER evaluating decisions with simulation evidence.
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: biomedical investigator
Decision: Your team must decide what the evidence from response analysis CER supports before submitting the claim-evidence-reasoning response named on today's page.
- • Judge your call against the decision log and what you knew then, not against how the patient ended up.
- • Mark the yellow tag as a bad decision, because the patient crashed and a good outcome means a good call.
- • Look up how severe that patient's injuries actually were before naming a protocol change, since severity and chance also shape outcomes.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about response analysis CER. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from response analysis CER supports before submitting the claim-evidence-reasoning response named on today's page.
Context: Grading your own decisions against recorded evidence, not against how you felt, is what turns one messy event into a better protocol for the next one.
- • T1: State a claim about whether the order optimized patient outcomes.
- • T2: Cite assessment data and categories as evidence.
- • T3: Explain reasoning that connects each decision to its outcome.
- • T4: Recommend one change to improve the response protocol.
- • T5: Identify assumptions and limitations from the simulation.
- • E1: Biomedical evidence supports a conclusion only to the level allowed by the measurement, comparison, controls, source quality, and uncertainty in the investigation.
- • E2: Define variables, controls, sampling, units, and the analysis plan before interpreting a result; analysis cannot repair biased or inconsistent measurement.
- • E3: Write a CER evaluating decisions with simulation evidence.
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Students often think whether a decision was good by whether the patient ended up okay, so a good outcome means a good decision. The trap: A patient can survive despite a poor call or die despite a correct one, because outcomes also depend on injury severity and chance. A CER evaluates the decision against the evidence and information available at the time, not just the final outcome.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.
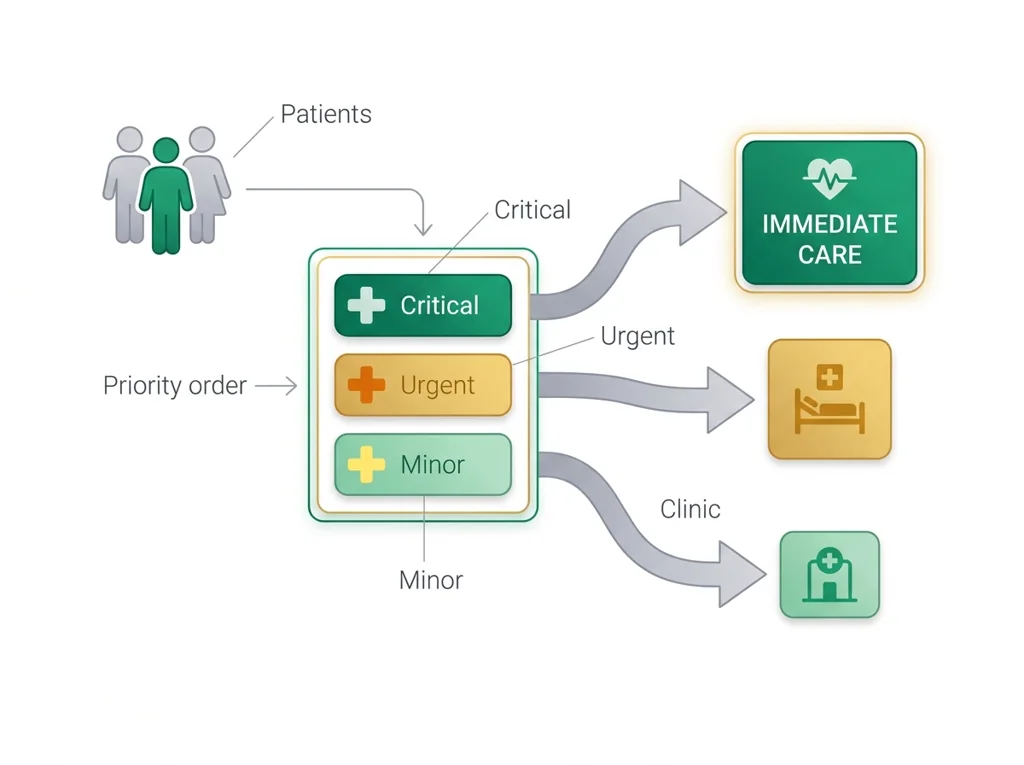
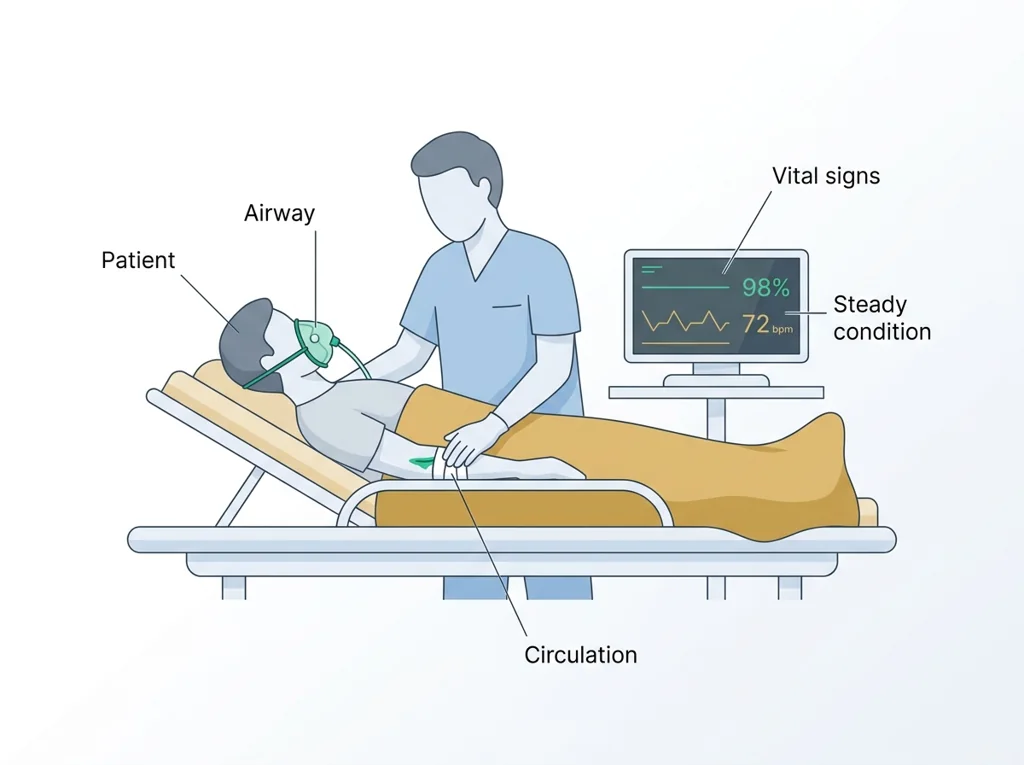
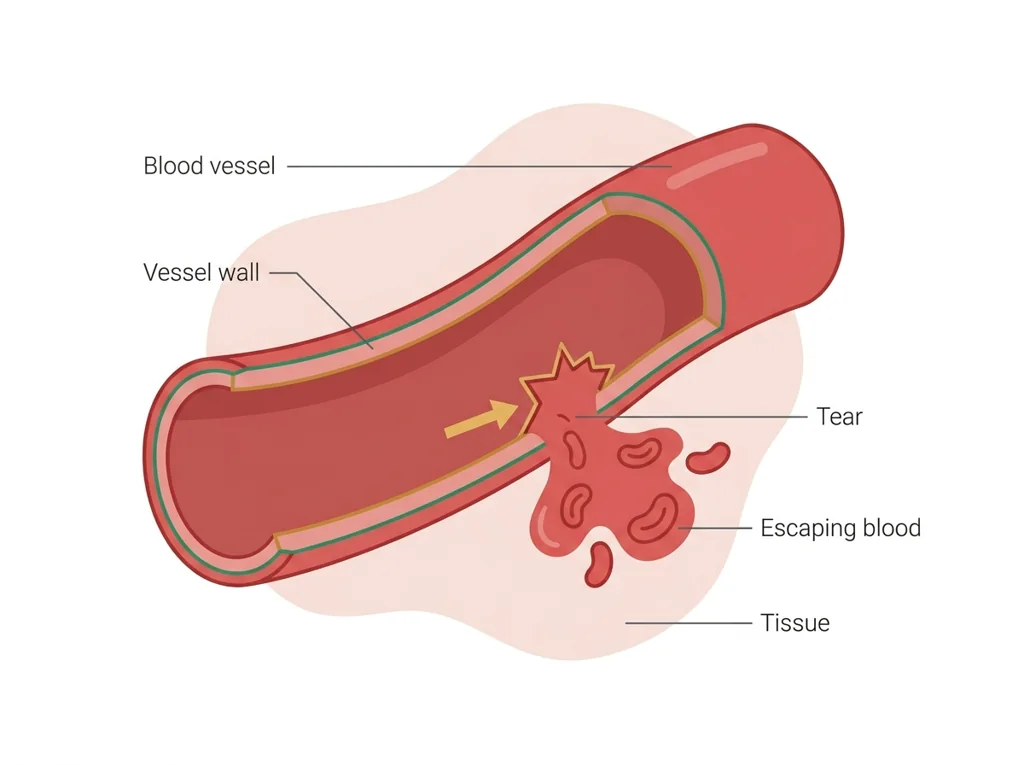
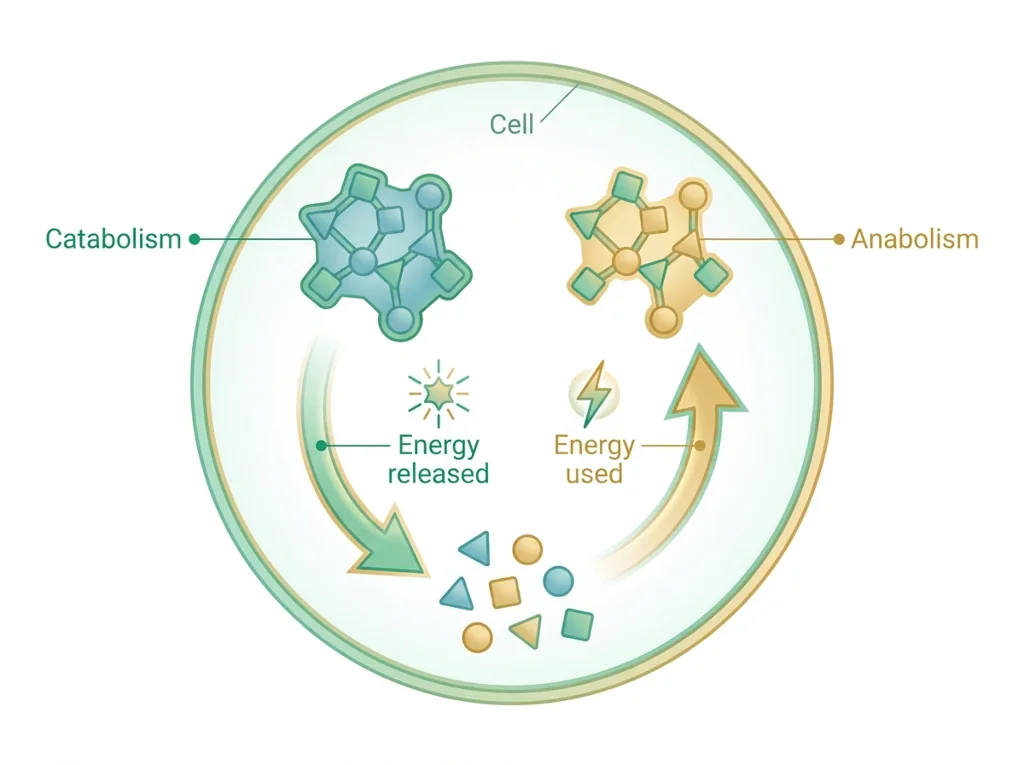
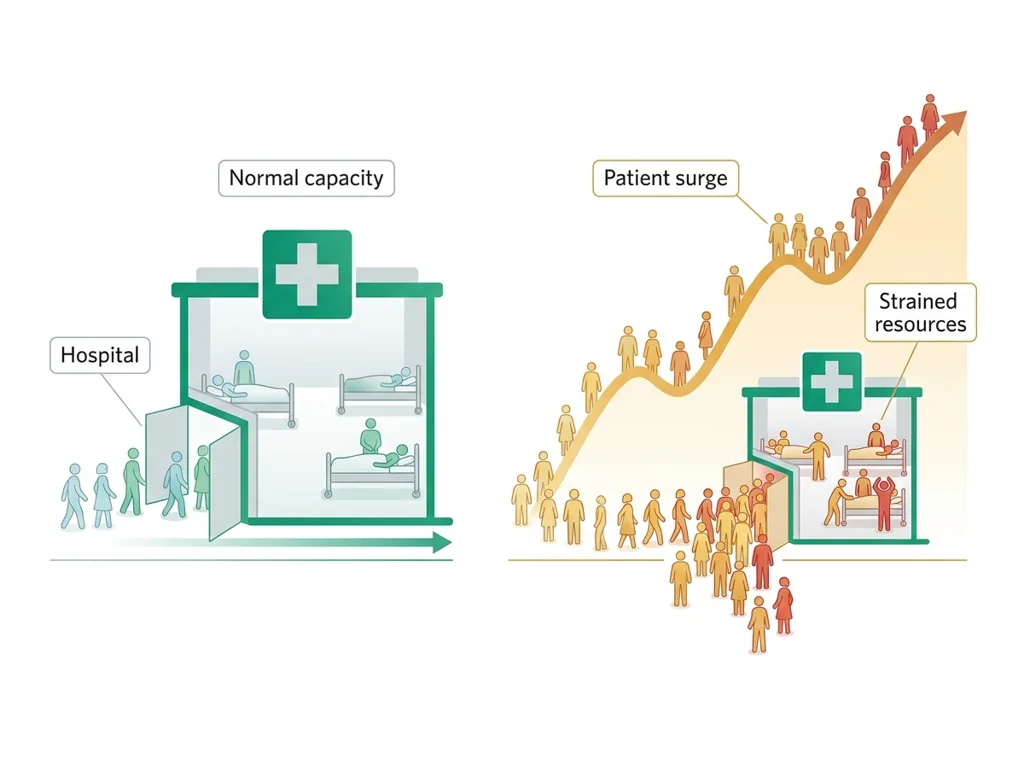
Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Response analysis CER. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
2.2 Start the work
State a claim about whether the triage order optimized patient outcomes.
Show all 5 required steps
- State a claim about whether the triage order optimized patient outcomes.
- Cite assessment data and triage categories as evidence.
- Explain reasoning that connects each decision to its outcome.
- Recommend one change to improve the response protocol.
- Identify assumptions and limitations from the simulation.
Lost your place? Make sure you have stated a claim about your triage order (step 1), cited assessment data and tags as evidence (step 2), explained the reasoning linking decisions to outcomes (step 3), recommended one protocol change (step 4), and named your assumptions and limitations (step 5).
- 0-8 minReview the simulation decision log: identify the decision you are most and least confident in.
- 8-20 minWrite the claim: one sentence stating whether the order optimized patient outcomes.
- 20-42 minWrite evidence: cite specific patient tags, assessment data, and timing from the log.
- 42-58 minWrite reasoning: connect each decision to its patient outcome.
- 58-70 minAdd protocol improvement recommendation and simulation limitations section.
- 70-80 min: confirm claim takes a position, evidence is decision-log specific, limitation is stated.
- • Last class you made decisions under time pressure; today you audit those decisions honestly.
- • Your CER claim should take a position: did the order optimize outcomes or not? Not 'it went okay.'
- • The improvement recommendation is the part that makes this CER useful: it closes the learning loop.
- • Simulation limitations remind readers that the conclusion may not transfer directly to a real mass-casualty event.
PLTW connection and today's work
In myPLTW, open Lesson 3.2 Emergency Response and go to Activity 3.2.4 Crisis Communication. Use it as the scaffold for your CER.
Today's stopping point: The myPLTW prompts done in the first 10 minutes; full CER submitted before end of period.
PLTW activity titles identify the course connection. If your account will not open, use the posted materials for today and tell Mr. Mendoza. Do not mark an online activity complete unless you completed it.
Course connection
- Activity 3.2.4 Crisis Communication
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
Worked CER on a parallel case (bystander CPR and AED response). This models the format and depth PLTW expects. It is NOT about today's triage question, so use it only to see how a strong response-analysis CER is built.
Claim: Our bystander response mostly optimized the outcome, but we lost about a minute of chest compressions while searching for the AED, and that pause was the weakest part of our response.
Evidence (from our action log): We confirmed the collapsed adult was unresponsive and not breathing normally at 0:20 and started compressions at 0:40. The log shows compressions stopped at 2:10 when one responder left to find the AED, and they did not restart until the AED arrived and analyzed the rhythm at 3:15. That is a gap of roughly 65 seconds with no compressions.
Reasoning: The chain of survival depends on high-quality, minimally interrupted compressions, because every pause lets blood flow to the brain and heart fall back toward zero. The guideline is to send a second person for the AED while the first keeps compressing, so circulation never stops. By having the only compressor leave to get the AED, we broke that rule and created exactly the kind of long pause the protocol is designed to prevent.
Recommended protocol change: Assign AED retrieval to a named second bystander before compressions begin, so the person doing compressions never has to stop to go get the device. This is specific and tied to the exact decision that cost us time.
Assumptions and limitations: This was a manikin drill with a training AED, so the pause had no real physiological cost and the manikin could not actually deteriorate. In a real cardiac arrest the same 65-second gap could meaningfully lower the chance of survival, which is why the change matters even though the drill still ended in a clean save.
This model shows the level of evidence and organization needed to complete: A parallel worked response-analysis CER for a different emergency scenario: it judges whether a bystander CPR and AED response optimized the outcome, cites a timed action log, recommends one specific protocol change, and states limitations. Use it as a format-and-depth model, not as an answer to today's triage prompt.
- Write one defensible claim.
- Choose specific evidence that supports the claim.
- Explain the scientific rule that connects the evidence to the claim.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Submit your CER in Schoology before end of period.
A research team lays out its question, variables, controls, sampling plan, measurement record, and analysis before deciding what the data support.
- Which variable is changed or compared?
- Which conditions and measurements must stay consistent?
- Which conclusion is inside the study's evidence boundary?
Define variables, controls, sampling, units, and the analysis plan before interpreting a result; analysis cannot repair biased or inconsistent measurement.
A well-organized classroom study can still be limited by , measurement quality, confounding, and the population represented.
- • Question and variable cards map to the study design.
- • Control and measurement cards map to fair, reproducible data collection.
- • The conclusion card maps to a bounded claim supported by the analysis.
Part 4 of 4 · Your work▸
Check your work before submitting
- Write a CER evaluating triage decisions with simulation evidence.
- Recommend an improvement and state at least one limitation.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- CER evaluating the simulation triage order, citing decision-log evidence, connecting decisions to outcomes, recommending one protocol improvement, and stating simulation limitations.
How to submit and name your file
Submit as one PDF in Schoology.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Today's lesson is in Schoology
Each school day has one lesson page in Schoology that holds everything for the day: the goal, the story so far, every table and data value, the numbered steps, and what to turn in. Open it first and work from it. The other rows for this day, if any, are the score line for a paper quiz or test and the John Carroll debate item; they do not add work. Check Schoology for each deadline.
- Today's Lesson · Mon 12/7 · Wk16 · Confirm the pathogen with the Gram stain, then plan your outbreak podcast(today's lesson page: the goal, the data, the steps, and what to turn in are all on it)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: Teams that follow a shared SOP with fixed roles tag and stabilize more patients under pressure, because assigned scope and a repeatable order prevent the missed assessments and duplicated effort that improvising produces. Today: You evaluate a triage decision against the logged evidence and the information you had, not against the final outcome, because outcomes depend partly on severity and chance, so only the evidence-based review reliably points to the next protocol improvement.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about response analysis CER. It cannot prove causation, diagnose a real patient, or justify action outside this room.
A team tagged a patient correctly by protocol, but that patient still died. In a CER, is that automatically evidence of a bad decision? Explain.
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
Today is individual work you can do from home: complete the same target above, then submit your CER.
Go to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
Ready.gov: know what to do in an emergencyThe optional extra-credit track is open. Complete reserved-unit work from home, including virtual labs, for extra credit. Each item shows its correct submission route.
Open the extra-credit trackSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Hand-picked readings and interactives for this lesson, from authoritative open organizations and PLTW's own public course outline.
This week
My Progress dashboard