
Human Body Systems · 2027-04-21 · 80 minutes
Wk14 Lab report: Heart model and EKG
Your goal: Build a heart-flow model and record an EKG and pulse to relate structure to function.
One product: Annotated EKG trace with P, QRS, and T waves labeled and linked to cardiac cycle phases, plus a data table recording resting pulse and blood pressure with units.
If access is unavailable, save a dated copy and tell the teacher. Ask for the actual laboratory, journal and official-task directions; do not substitute example values for your own assigned evidence.
Start the work
- Label the supplied blood-flow schematic. Follow the teacher's separate directions and supervision for actual model assembly or testing.
- Trace the complete chamber-and-valve route on paper and explain each one-way connection.
- Annotate P, QRS and T on the constructed trace and use the exact supplied timing inputs; do not claim a resting recording.
- Complete the separate original pulse-count and blood-pressure notation exercises; leave actual measured values blank until teacher-confirmed work.
- Link the electrical events to the supplied phase/valve table and state limits on timing, pressure and clinical claims.
Show the 80-minute plan
- 0 to 10 minutes. Read H1 and P1, define terms and answer warmups.
- 10 to 22 minutes. Label V1 and demonstrate every arrow on paper.
- 22 to 42 minutes. Annotate V2 and compute two intervals and rate.
- 42 to 55 minutes. Complete count and notation exercises; preserve blank authentic fields.
- 55 to 68 minutes. Complete phase table and self-check; apply the R1 fact.
- 68 to 80 minutes. Reflect, check the full record and identify your next action; extend if ready.
Open your materials
Use the reading, word guide, and worked example below. Keep your answers on paper or in one document.
Printable lesson and response record (PDF). This packet contains the same required reading and work.
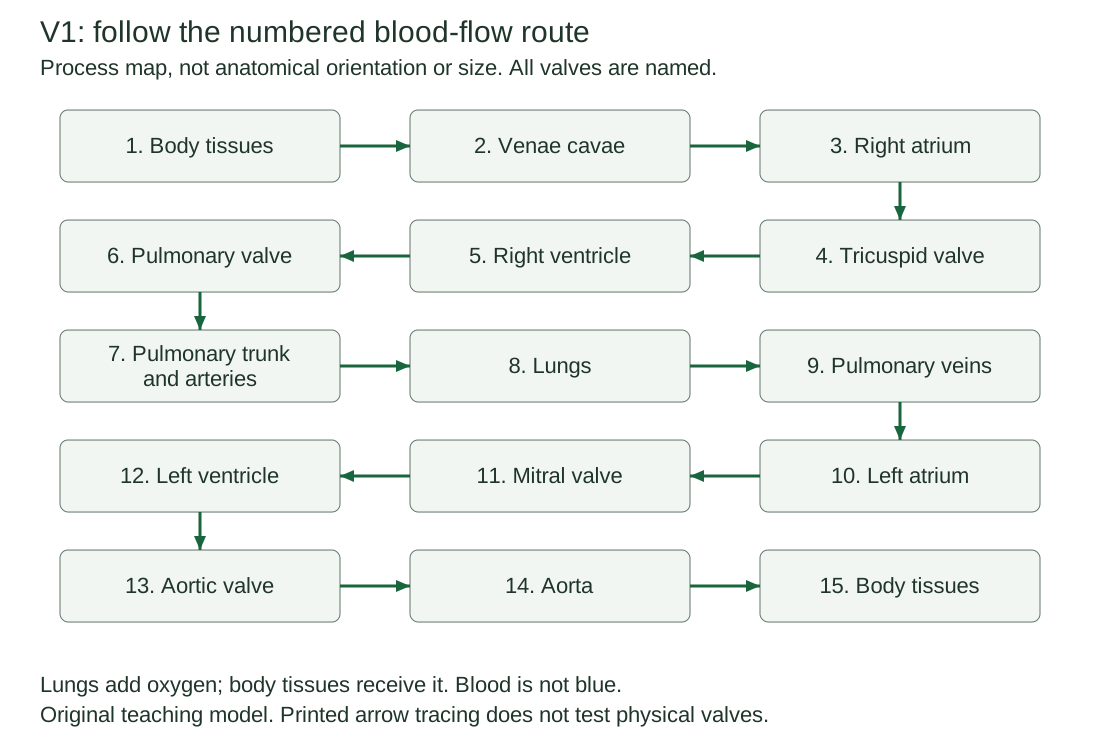
V1: complete original blood-flow route
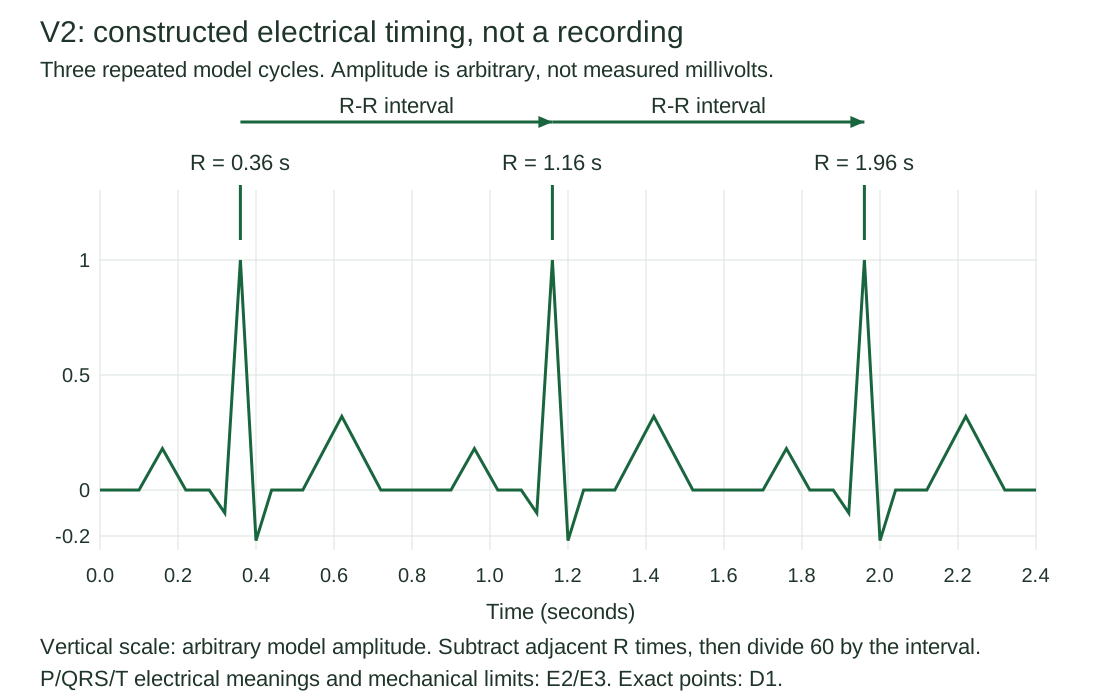
V2: constructed ECG timing model
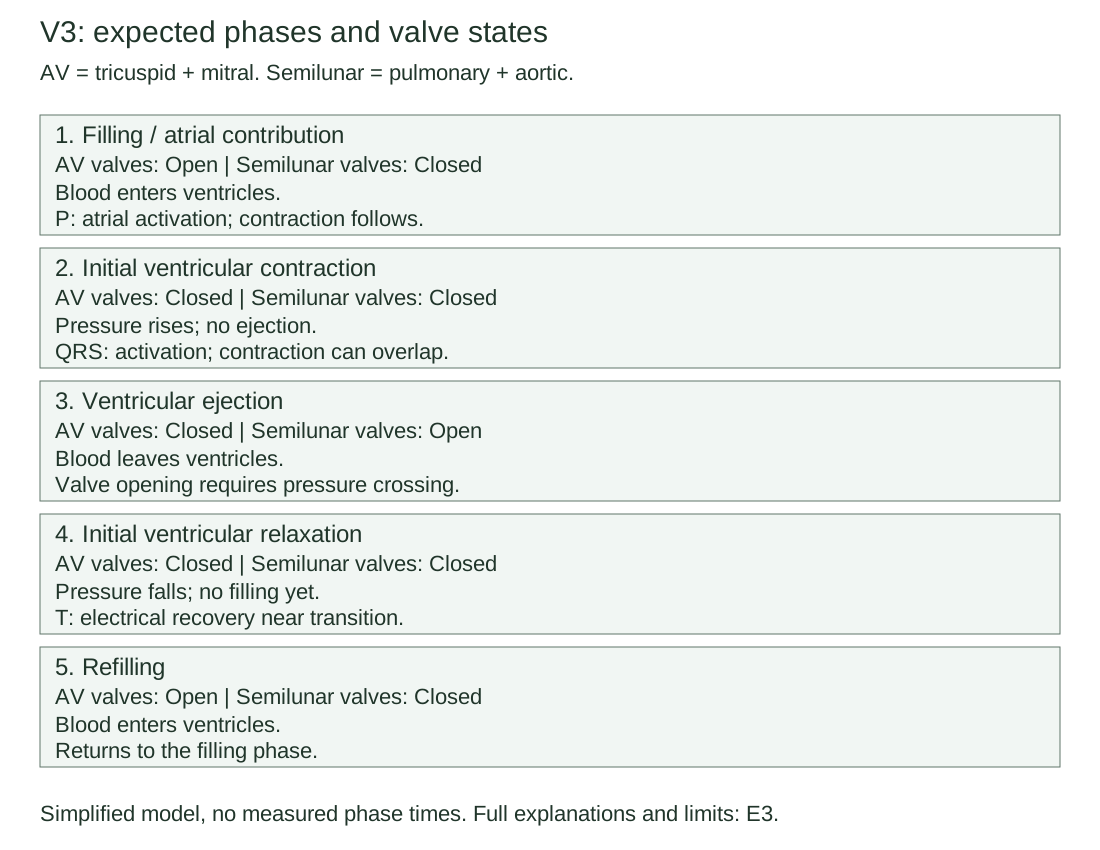
V3: expected phases and valve states
Question: What can a constructed electrical trace explain about the cardiac cycle, and which measurements does it not supply?
Words you will use
- atrium
- A heart chamber that receives returning blood.
- ventricle
- A heart chamber that pumps blood into an outgoing artery.
- venae cavae
- The large veins returning blood from the body to the right atrium.
- tricuspid valve
- The valve between the right atrium and right ventricle.
- mitral valve
- The valve between the left atrium and left ventricle.
- pulmonary valve
- The valve between the right ventricle and pulmonary trunk.
- aortic valve
- The valve between the left ventricle and aorta.
- aorta
- The main artery carrying blood from the left ventricle to the body.
- pulmonary arteries
- Vessels carrying blood away from the right heart toward the lungs.
- pulmonary veins
- Vessels returning blood from the lungs to the left atrium.
- artery
- A vessel carrying blood away from the heart.
- vein
- A vessel carrying blood toward the heart.
- capillary
- A small blood vessel where exchange with surrounding tissues occurs.
- pulmonary circulation
- The blood route between heart and lungs.
- systemic circulation
- The blood route between heart and the rest of the body.
- oxygenation
- Adding oxygen to blood.
- valve
- A structure that helps prevent backward flow.
- AV valves
- The atrioventricular valves: tricuspid and mitral.
- semilunar valves
- The pulmonary and aortic valves at the ventricular outlets.
- ECG / EKG
- Electrocardiogram: a recording of the heart’s electrical activity at the body surface.
- electrode
- A contact used to detect electrical signals.
- lead
- An electrical view formed by a defined electrode arrangement.
- depolarization
- A change in cell membrane electrical state associated with activation.
- repolarization
- Return of membrane electrical state toward its resting condition.
- P wave
- The ECG wave representing atrial depolarization.
- QRS complex
- The ECG deflections representing ventricular depolarization.
- T wave
- The ECG wave representing ventricular repolarization.
- R peak
- The prominent positive deflection within the constructed QRS complex.
- SA node
- The usual starting site of the heart’s electrical activation.
- AV node
- A conducting region that delays activation before it reaches the ventricles.
- His bundle
- The conducting bundle carrying activation from the AV node toward ventricular branches.
- Purkinje network
- Conducting fibers distributing activation through ventricular muscle.
- cardiac cycle
- The repeating sequence of cardiac filling, contraction, ejection and relaxation.
- systole
- The contraction phase of a heart chamber.
- diastole
- The relaxation phase of a heart chamber.
- ejection
- Movement of blood out of a ventricle into its outgoing artery.
- isovolumic
- Occurring without a change in chamber volume.
- pressure
- Force distributed over an area.
- blood pressure
- Pressure of blood against vessel walls.
- systolic pressure
- The higher arterial pressure associated with the pumping phase.
- diastolic pressure
- The lower arterial pressure between pumping phases.
- mmHg
- Millimeters of mercury, a unit of pressure.
- pulse
- A pressure wave in arteries associated with heart ejection.
- bpm
- Beats per minute, a unit of rate.
- R-R interval
- Time between adjacent R peaks.
- rate
- The number of events per unit of time.
- amplitude
- The vertical size of a plotted signal relative to its reference.
- arbitrary units
- A declared model scale that is not a calibrated physical measurement.
- millivolt
- One thousandth of a volt, a unit of electrical potential difference.
- stroke volume
- The volume ejected by a ventricle in one beat.
- cardiac output
- The volume pumped by a ventricle per minute.
- artifact
- A signal feature arising from the measurement process rather than the target activity.
- calibration
- Relating instrument output to known values on a defined scale.
- schematic
- A simplified representation emphasizing selected relationships.
- constructed
- Deliberately drawn or calculated for this original exercise.
- authentic record
- Evidence from work actually performed, with its method and source identified.
- uncertainty
- A limit on what is known or can be concluded.
- heart failure
- A condition in which the heart cannot pump enough blood to meet the body’s needs.
- arrhythmia
- A problem with the rate or rhythm of the heartbeat.
- prediction
- An expectation stated before checking the result.
H1: original practice and actual laboratory boundary
Today’s original recovery uses paper diagrams and constructed timing inputs. It records no person’s heart activity. The actual model, recording, pulse and blood-pressure tasks remain open until teacher-confirmed work is performed.
Use no electrodes, cuff, sensor or exercise procedure from this lesson. The actual device manual, equipment check, teacher supervision and participation or alternative route must be confirmed separately.
The class list names an EKG device, personal disposable pads, BP equipment, pulse oximeter, heart model, notebook, ruler and timer. A picture does not establish that these are available.
Keep actual recordings and health information in the teacher-approved private route. Do not put medical histories or identifiable measurements into this original record or a public class discussion.
Blank authentic record template: leave spaces for date/condition, model demonstration, device and method, resting ECG file and time scale, and quality note. Add only observations and methods from the actual assigned work.
Actual resting pulse: leave the value blank; unit bpm. Add the method and counting duration only from the actual assigned work. Actual blood pressure: leave systolic and diastolic values blank; unit mmHg. Add the device and method only from the actual assigned work.
Keep actual identity and health results only in the teacher-approved private record. Use this public practice record for checks and next actions; do not enter participant results.
Original record labels are MODEL, COUNT EXERCISE and NOTATION EXAMPLE. The separate authentic record starts blank. Leave missing or invalid measurement fields blank and explain the missing evidence; never fill them with the examples.
E1: a full blood-flow route
NHLBI explains that veins bring blood toward the heart and arteries carry it away. These names describe direction, not oxygen content. Valves help prevent backward flow.
Trace V1 in numbered order: body tissues, venae cavae, right atrium, tricuspid valve, right ventricle, pulmonary valve, pulmonary trunk and arteries, then lungs.
Continue: pulmonary veins, left atrium, mitral valve, left ventricle, aortic valve, aorta, then body tissues again. Venae cavae means the large returning veins.
The pulmonary route carries blood between heart and lungs. The systemic route serves the rest of the body. Oxygen-poor and oxygen-rich are relative labels; blood is not blue.
In the simplified model, oxygen enters blood at the lungs and is delivered to body tissues. V1 uses an ordered route, not an anatomical front view or a model of exact vessel size.
Trace each arrow with a finger or paper token, name all four valves and explain the direction each permits. This demonstrates the printed sequence, not tested physical valve action.
E2: electrical events and expected mechanical effects
An ECG or EKG records changing electrical potential differences at the body surface. MedlinePlus states that it records electrical signals; it does not send electricity into the body.
OpenStax identifies P as atrial depolarization, QRS as ventricular depolarization and T as ventricular repolarization. Depolarization initiates activation; repolarization is electrical recovery, not a direct pressure measurement.
Electrical activation begins before the resulting contraction. The events overlap: ventricular contraction can begin during QRS, around the R peak in the textbook model. Do not wait until the entire QRS ends.
In the usual sequence, the SA node initiates activation, the atria activate, an AV-node delay occurs, and the His bundle, branches and Purkinje network distribute activation through the ventricles.
The ECG is not a picture of blood flow, force or valve movement. Its waves cannot provide a cuff blood pressure, stroke volume or a diagnosis from this classroom exercise.
E3: five phases and valve states
V3 supplies a simplified phase table. AV valves means tricuspid and mitral; semilunar valves means pulmonary and aortic. Valve opening depends on pressure differences, not an electrical command to the valve.
Phase 1, filling and atrial contribution: AV valves open; semilunar valves closed. Blood enters ventricles. P represents atrial activation, followed by atrial contraction near the end of filling.
Phase 2, initial ventricular contraction: both valve groups closed. Ventricular pressure rises without ejection. QRS represents activation; contraction begins during that electrical sequence in the usual model.
Phase 3, ventricular ejection: AV valves closed; semilunar valves open. Pressure in ventricles exceeds the outgoing arteries, so blood leaves. The ECG alone does not measure this pressure crossing.
Phase 4, initial ventricular relaxation: both valve groups closed. Pressure falls before filling resumes. T represents ventricular electrical recovery around the transition toward relaxation.
Phase 5, refilling: AV valves open; semilunar valves closed. Ventricular pressure has fallen below atrial pressure and filling resumes. The cycle returns to phase 1.
This table connects expected events. It does not assign measured millisecond boundaries or show that any real participant’s valves opened correctly. Filling and ejection are not interchangeable.
D1: exact constructed timing and separate notation inputs
V2 is a constructed waveform, not an ECG recording. Its horizontal axis is seconds; its vertical axis is arbitrary model amplitude, not measured millivolts. The drawing uses three repeated model cycles.
R peaks are at 0.36, 1.16 and 1.96 seconds. Subtract each R time from the next R time to find each R-R interval.
For this regular constructed sequence, electrical rate equals 60 seconds per minute divided by the R-R interval in seconds per cycle, giving cycles per minute. This is arithmetic on a drawing.
One cycle uses these time/amplitude points: (0, 0), (0.10, 0), (0.16, 0.18), (0.22, 0), (0.28, 0), (0.32, -0.10), (0.36, 1.00), (0.40, -0.22), (0.44, 0), (0.52, 0), (0.62, 0.32), (0.72, 0), (0.80, 0).
Repeat that sequence with time offsets 0.80 and 1.60 seconds. Use E2 to decide which deflections are P, QRS and T before you mark them.
Separate invented pulse-count exercise: 36 pulses are stipulated over 30 seconds. Rate equals count divided by duration in seconds, times 60, giving beats per minute. No person was counted.
Do not compare the count-exercise rate with the model rate as a real pulse deficit: these are unrelated invented exercises. Record the input type and method beside each result.
Notation example only: 120/80 mmHg. Label 120 systolic and 80 diastolic. NHLBI explains systolic as pressure during pumping and diastolic as pressure between beats during filling.
The notation example is neither a measurement nor a universal normal target. A real BP value needs a suitable instrument and method; it cannot be calculated from the displayed ECG.
C1: warmups, application, self-check and extension
Warmup 1: does QRS relate to electrical activation before or during the onset of ventricular squeezing, or is it a direct picture of filling? Explain your initial choice.
Warmup 2: in the hypothetical 120/80 notation, which number names pressure during pumping? Record a prediction before using D1. No personal pressure is requested.
Prerequisite: name four chambers and trace the E1 route. Yesterday is not evidence that you already completed anatomy work; the full sequence is supplied here.
On-grade original task: label V1, demonstrate its arrows, annotate P/QRS/T on V2, compute both R-R intervals and the count-exercise rate, then link all three waves to E3.
Recovery: begin with the three wave names and their electrical meanings in E2. Then return to the full route, timing, notation and phase table. The smaller start does not waive the complete record.
Self-check: what does QRS represent, and how does activation relate to ventricular contraction onset? State the order without claiming the whole electrical complex must finish first.
Check method: use E2 to name the electrical event QRS represents, then use E3 phase 2 to place contraction onset relative to it. Finish by naming what the trace cannot measure.
Original extension: constructed model B has R-R intervals of 0.60 seconds; model A uses your D1 interval. Compute both rates and explain what changes. There was no exercise or participant.
Check: model B gives 100 cycles per minute, versus your D1 rate for A. Shorter intervals mean a faster electrical rate. Without stroke volume, blood volume pumped per minute remains unknown.
The actual rest-versus-activity extension needs teacher-confirmed participation, procedure and data. No exercise prescription is supplied. Explain the model comparison instead and ask for the actual assigned inputs.
Lost your place? Complete the route, three wave labels and both timing intervals first. Then use E3 for the phase explanation and H1 for any missing authentic results.
R1: a required health-source fact and an evidence limit
MedlinePlus Heart Diseases describes heart failure as the heart being unable to pump enough blood to meet the body’s needs. It also identifies arrhythmia as a problem with heartbeat rate or rhythm.
Use one of those two supplied facts in your final explanation. Connect it to why electrical timing and effective pumping are related but different questions.
The facts do not diagnose a model waveform or a student. A regular-looking drawing cannot prove adequate blood supply, and a strange classroom signal cannot be dismissed as harmless noise.
MedlinePlus explains that an ECG is a brief snapshot and a clinician may need other tests. Actual interpretation depends on the clinical situation and professional review.
Reflection: compare your prediction with the supplied model result, name an uncertainty and revise one sentence that confused electrical activity with pressure or pumping. Never claim an actual recording occurred.
P1: Official tasks and preparation checks
Today’s goal still requires a heart-flow model, resting EKG, pulse and blood pressure. Use this paper work for practice and ask for the actual task materials and records before doing those tasks.
Activity 3.1.1 Go With the Flow introduces cardiovascular structures and blood paths. Its navigation includes heart/model, vessel and oxygen-route sections and Conclusion, with separate Conclusion Questions.
Activity 3.1.3 Stayin’ Alive? introduces conduction, recording and interpretation. Its materials list Vernier Go Direct EKG sensor and pads, Graphical Analysis, markers and optional alcohol wipes.
That list does not verify the equipment in our classroom. Later device directions remain needed. No electrode position, cuff inflation, exercise or cleanup instruction is established by this page.
The 3.1.3 navigation includes Getting to the Heart of the Matter, Evaluation Through EKGs, Record Your Rhythm, Funky Rhythms and Conclusion. Travel Journal pages 5/6 and separate Conclusion Questions remain assigned inputs.
Travel Journal: https://instructional-resources.pltw.org/PLTW_Biomedical_Science/40211_HumanBodySystems/unit3/New_Zealand/page-5-6.html . The assigned journal text is not reproduced here; ask for it before answering its prompts.
Confirm the teacher’s assigned portions of 3.1.1 and 3.1.3. Retain the actual model, trace and readings, with a note or screenshot from the assigned work, for the tracker. Viewing badges do not prove performed work.
Before April 21, 25 minutes of Heart structure and cycle preparation in Lab Notebooks was assigned. If you have not done it, ask the teacher for the selected reading or demonstration.
April 19 covered allocation ethics; April 20 was a catch-up day. Do not assume yesterday’s anatomy model or prior work is complete.
The April 19-23 week also requires the cardiovascular data check and Friday evidence through 3.1.3. Teacher-posted data/model and selected Khan/EKG resources remain needed for the weekly absence route.
April 22 uses cardiac data for a CER. Keep today’s original inputs separate from any actual readings. April 23 lists 25-minute tracker/evidence preparation in Class Records.
Submit Wk14 Lab report: Heart model and EKG through the confirmed enrolled section. Section 1292: https://app.schoology.com/assignment/8544591414 . Section 6792: https://app.schoology.com/assignment/8544591449 .
If access is unavailable, save a dated practice record and tell the teacher. Check Schoology after uploading. The actual async resting ECG/pulse task cannot be fulfilled by calling V2 a recording.
M1: different worked timing inputs
This separate constructed model has R peaks at 0.25, 1.25 and 2.25 seconds. Adjacent intervals are each 1.00 second; electrical rate is 60/1.00, or 60 cycles per minute.
A separate invented count is 15 pulses in 20 seconds. Rate is 15/20 times 60, or 45 beats per minute. It describes no person and is not paired with the constructed trace.
I label the units and source of each result. Different invented inputs cannot establish a real mismatch, health condition or exercise response.
For the learner task, use D1’s different times and count. Identify each wave’s electrical meaning, then use E3 to explain the expected mechanical sequence instead of reading pressure from a peak.
Try the decision
Which statement fits the supplied original trace and phase evidence?
- QRS represents ventricular activation; contraction can begin during it, and the trace alone supplies no blood-pressure value.
- The complete QRS must end before any ventricular contraction begins, so every peak marks a pressure spike.
- Regular spacing in the drawing and its calculated rate prove that the participant’s heart pumps normally.
Explain your choice using the reading. Discuss it or say it to yourself. This practice does not add another submission.
Your response record
Use these labels on paper or in your document. The space below also works when this page is printed.
Readiness and prediction
Use H1 and P1 to list actual missing inputs. Answer both C1 warmups and predict which quantity the ECG device and blood-pressure cuff would each record.
Read definitions first. Use no participant data; the authentic branch begins with blank fields.
Build the original flow model
Label V1, trace all directed connections and name the four valves. Explain which valve group permits filling and which permits ejection.
E1 supplies every label. A traced paper route does not certify an actual physical model.
Annotate the constructed ECG
Mark P, QRS and T on V2. Record all three R times, compute both R-R intervals and derive the model rate with units.
D1 contains exact values. Amplitude is arbitrary and the figure is not a recording. Use M1 for a different worked example.
Keep timing, pulse and pressure separate
Calculate the D1 count-exercise rate and label both numbers of the notation example. Leave actual pulse, BP, device and quality fields blank until their own observations and methods are available.
The count-exercise rate and the model rate are unrelated exercises, not paired clinical measurements. ECG cannot supply a cuff pressure.
Connect electrical and mechanical events
Complete all five phase/valve rows, answer C1’s self-check and use one R1 MedlinePlus Heart Diseases fact in your explanation.
Explain activation before contraction onset with overlap, pressure-driven valve opening, and why a regular trace does not prove effective pumping.
Reflect and check your evidence
Compare your prediction to the supplied model, name a limit and revise one overclaim. Complete the full original record; use C1’s optional model-period comparison when ready.
Use the assigned async recording, physical model and measurement directions separately. Request missing official journal or conclusion prompts, and check Schoology after uploading.
Check your product
- Model correctly shows one-way flow through valves.
- EKG waves are linked to cardiac cycle phases.
- Original diagrams and calculations are labeled as constructed practice, with both timing intervals and units.
- The explanation uses a supplied MedlinePlus Heart Diseases fact and distinguishes electrical events, pressure and pumping.
- Leave actual data fields blank without their own observations. Ask for official-task directions and ways to take part in required class activities.
Original constructed diagrams and calculations support educational structure, timing and notation reasoning. They cannot establish actual ECG, pulse, blood pressure, physical model performance, diagnosis, exercise response, official completion or submission.
Turn in your work
Wk14 Lab report: Heart model and EKG
Submit the labeled original practice record to the confirmed enrolled section: 1292 https://app.schoology.com/assignment/8544591414 or 6792 https://app.schoology.com/assignment/8544591449 . Keep actual model/recording/vitals and official tracker evidence separately identified.
- Section 1292: Wk14 Lab report: Heart model and EKG
- Section 6792: Wk14 Lab report: Heart model and EKG
If access is unavailable, save a dated copy and tell the teacher. Ask for the actual laboratory, journal and official-task directions; do not substitute example values for your own assigned evidence.
Connection to PLTW
Original paper practice; the actual heart-model, recording and vitals tasks remain separate assigned work.
These references locate related course material. Complete only the official work and stopping point your teacher assigns. This local preparation does not establish completion of an online activity.
- Activity 3.1.1 Go With the Flow
- Activity 3.1.3 Stayin' Alive?
Optional practice and examples
Use these resources to practice related skills. Follow the required work and evidence limits above. A simulation does not authorize a live experiment or add another submission.
Slides and optional notes
Keep complete flow labels, three wave labels, two R-R intervals and rate, count/notation exercises, five phase rows, MedlinePlus fact, self-check and record of checks and next actions together. Original values never fill authentic result fields. Guided notes are optional and do not add a second submission.
Sources and optional reading
- How Blood Flows through the Heart · NHLBI
- Anatomy and Physiology 2e: 19.2 Cardiac Muscle and Electrical Activity · OpenStax, Rice University
- Anatomy and Physiology 2e: 19.3 Cardiac Cycle · OpenStax, Rice University
- Electrocardiogram · MedlinePlus, National Library of Medicine
- Heart Diseases · MedlinePlus, National Library of Medicine
- What Is High Blood Pressure? · NHLBI; used for pressure notation only
Keep going
If you were absent or lost your place, read the word guide and reading first. Try the example, then complete the first unfinished response.
No partner is required. Read your response aloud to yourself and check it against the product checklist.
Take home: Electrical activation precedes and overlaps the onset of pumping; a trace can support timing claims without measuring blood pressure or proving effective blood flow.
Carry the labeled original model and its limits into the next analysis. Keep actual recordings and measurements separate from the supplied examples; use only records from work actually performed. Which measured quantity would be needed to test the model's prediction?