
Clinical diagnosis team project
This page has four parts, in the order you use them. Part 1 is what you need to know. Part 2 says what to do, in plain English. Part 3 shows the work done once on a case that is not yours. Part 4 is your own work and where to turn it in.
Open your materials, follow the steps, then turn in your work.
Student teams synthesize patient data to propose and justify a working diagnosis.
Check you have the right sheet: the top of it prints today's portal day, Clinical diagnosis team project. The PLTW activity itself is in myPLTW and is not posted here.
Optional: listen or watch a unit review▸
Part 1 of 4 · Background and definitions▸
💡 Big idea: A team using a shared, ordered evidence table catches blind spots a lone reviewer misses, so combining people and data sources makes the diagnosis more accurate.
- • A shared evidence table organizes all workup data so the team can compare findings systematically.
- • A ranked differential lists candidates from most to least likely, with data supporting each rank.
- • Each team member owning a section of the recommendation distributes accountability and reduces blind spots.
A pedigree feeds parental genotypes into a Punnett square, so a family's history becomes a quantified probability instead of a rough estimate.
A team using a shared, ordered evidence table catches blind spots a lone reviewer misses, so combining people and data sources makes the diagnosis more accurate.
Driving question: Your team has one full of history, vitals, bloodwork, and genetics. Following a fixed review order, which values are out of range, and what is your ranked differential with the most likely candidate on top?
What you already know: A pedigree feeds parental genotypes into a Punnett square, so a family's history becomes a quantified probability instead of a rough estimate.
New idea: A team using a shared, ordered evidence table catches blind spots a lone reviewer misses, so combining people and data sources makes the diagnosis more accurate.
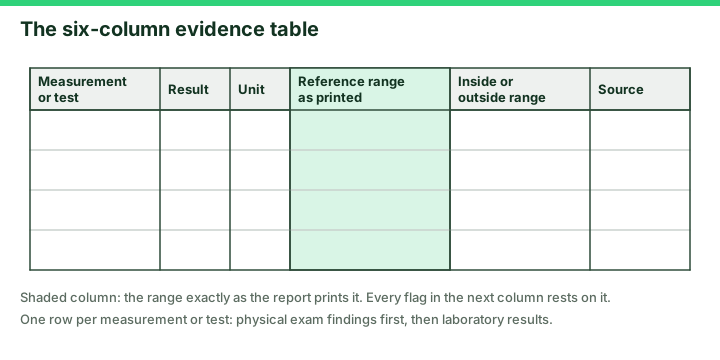
- Observe or measure the relevant feature in clinical diagnosis team project.
- Organize the observation with a stable evidence ID.
- Apply this rule: A screening signal changes what to investigate next; it does not automatically prove the cause.
- Choose the option the evidence supports and state the limit of the conclusion.
Real biomedical example: Your team has one full of history, vitals, bloodwork, and genetics. Following a fixed review order, which values are out of range, and what is your ranked differential with the most likely candidate on top?
What the evidence supports: E1 to E3 and the figure support the daily take-home when the response meets the stated success criteria.
What it cannot prove: The package does not support claims beyond this lesson's or any real patient diagnosis.
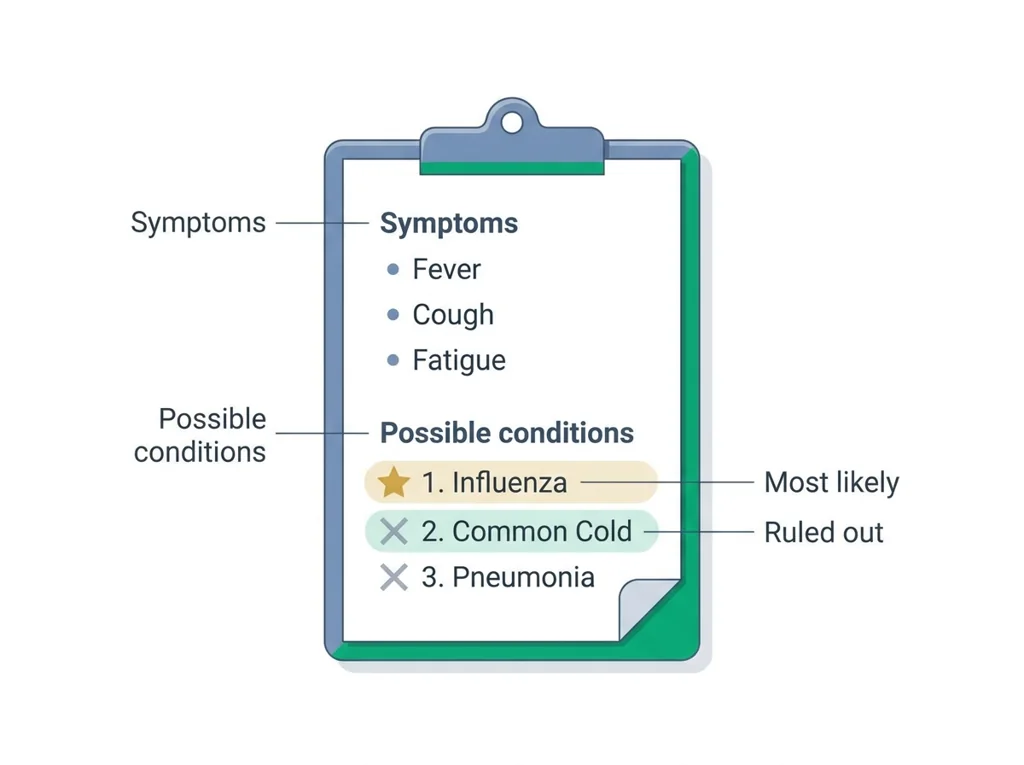
- • : The ranked list of conditions that could explain a patient's story. The whole game is narrowing it honestly.
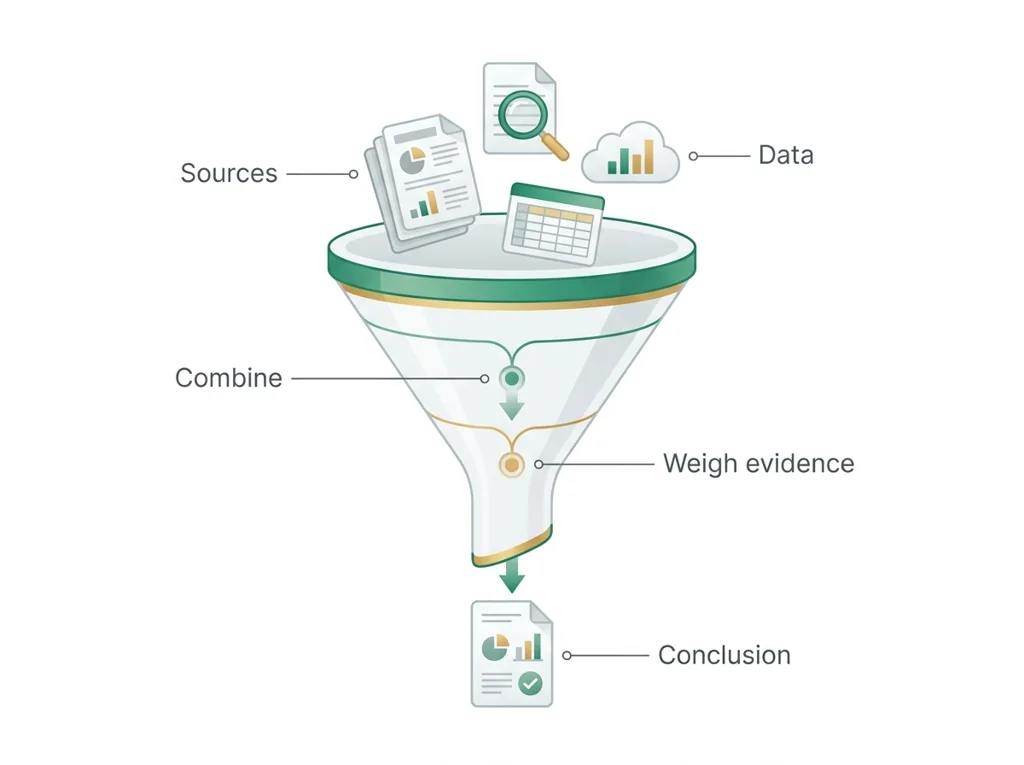
- • : Combining findings from many separate sources into one organized conclusion, weighing how strong and consistent the evidence is overall.
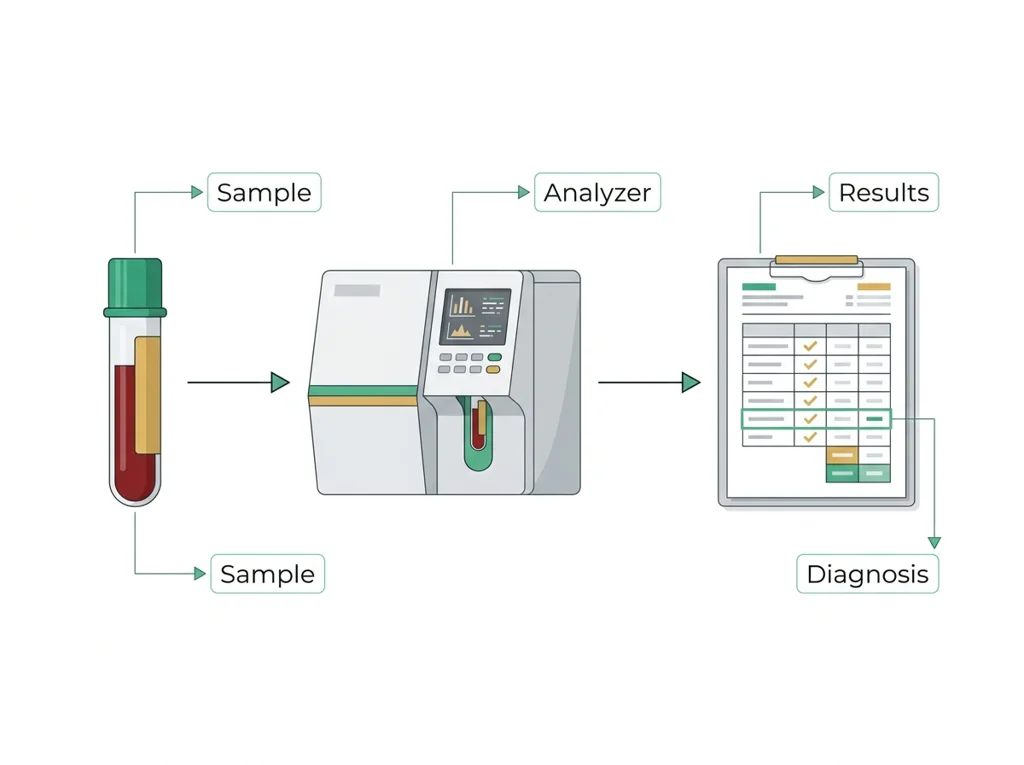
- • : A procedure that analyzes a sample of blood, urine, or to provide measurable information that helps diagnose or monitor a condition.
- • : An organized record of a patient's medical history, test results, medications, and care, used by the healthcare team to make decisions.
- • recommendation: A clear, evidence-based suggestion for what action to take, drawn from analyzing data, results, or a patient's situation.
Use it now: Choose one decision option. Cite E1 and E3, then explain how the rule connects the evidence to your choice. This is thinking practice for the one turn-in named under Turn in, not a second submission.
Go further, optional: The source links below are optional enrichment. Every fact required for today's local evidence decision appears in this lesson package.
A classroom clinical recommendation must connect case findings to a plausible mechanism, expected benefit and harm, alternatives, and uncertainty without presenting the composite case as a real diagnosis or prescription.
Limit: The classroom case omits clinical history, examination, validated testing, patient preferences, and professional judgment needed for real care.
A screening signal changes what to investigate next; it does not automatically prove the cause.
Limit: Biomedical tests have measured performance and biological sampling limits that a household alarm does not capture.
Team produces a ranked differential grounded in the full data set.
Limit: E3 defines the classroom product or success criterion. It is not independent scientific evidence and cannot justify a clinical or causal claim.
Today's decision · Simulated classroom evidence scenario
Your role: biomedical investigator
Decision: Your team must decide what the evidence from clinical diagnosis team project supports before submitting the labeled and result claim named on today's page.
- • Hold the ranking until a repeat set of labs shows whether the out-of-range values are moving or steady.
- • Build one shared evidence table so history, vitals, labs, and genetics are compared together before ranking the differential.
- • Split the chart by section so each teammate reviews one, then combine the four findings into the final diagnosis.
Response: State one choice, cite at least two evidence IDs, explain the rule that connects them, and add one limitation. Use it inside the one turn-in named under Turn in; it is not a separate submission.
Claim ceiling: Today's evidence supports a classroom claim about clinical diagnosis team project. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Reason for review: Your team must decide what the evidence from clinical diagnosis team project supports before submitting the labeled and result claim named on today's page.
Context: Clinical diagnosis improves when multiple people synthesize multiple data sources, because a shared, organized process catches the blind spots any single reviewer would miss.
- • T1: As a team, define the for reviewing a in a fixed order.
- • T2: Identify which variables in the chart are normal and which are out of range.
- • T3: Combine history, vitals, bloodwork, and genetics into a shared evidence table.
- • T4: Generate a ranked and select the most likely candidate.
- • T5: Assign each member a section of the recommendation and note data limitations.
- • E1: A classroom clinical recommendation must connect case findings to a plausible mechanism, expected benefit and harm, alternatives, and uncertainty without presenting the composite case as a real diagnosis or prescription.
- • E2: A screening signal changes what to investigate next; it does not automatically prove the cause.
- • E3: Team produces a ranked differential grounded in the full data set.
Measurements: Use only the measurements, units, graph, or counts supplied in today's task. No additional patient measurement is implied.
Figure finding: An empty table with six columns, Measurement or test, Result, Unit, Reference range as printed, Inside or outside range and Source, four blank rows, and the reference-range column shaded, with notes that every flag rests on the printed range and that physical exam findings come first.
Uncertainty: This is a composite classroom scenario. Missing history, measurements, or confirmation tests remain unknown and limit the conclusion.
Difference = 14.0 minus 13.5 = 0.5 g/dL below the lower limit. The table row gets the value, the unit, the range exactly as the report prints it, and the flag below range by 0.5.
A practice value, made up for this example and not from your newborn's results, reads 13.5 g/dL, and the range printed beside it is 14.0 to 24.0. How far outside the range is it, and what goes in the evidence table?
Take every range from the report in front of you, never from memory (your 2.3.1 sheet shows where each one goes); newborn ranges differ from adult ranges. A value inside the range gets within range and no flag.
For each chart value, write it with its unit, the printed range, and a flag only when it sits outside that range; the flags are what your ranked differential rests on.
Students often think dividing the work means each teammate looks at only their own section and the diagnosis is just stapled together at the end. The trap: a diagnosis comes from combining sections, not isolating them. The evidence table exists so every teammate sees how history, vitals, labs, and genetics line up together; splitting ownership of the writeup is about accountability, not about reviewing the data in silos.
- CER:
- Claim, Evidence, Reasoning: make a claim, back it with evidence, explain your reasoning.
- SOP:
- Standard Operating Procedure, the exact steps to follow (especially in a lab).
- Tracker:
- Your PLTW progress log where you record completed evidence.
- myPLTW:
- The PLTW course site where you do the online activities. Find it in Clever with your Microsoft sign-in, right next to Schoology.

Tap the speaker to hear a term. Add two of these to your notebook glossary with a definition and an example in your own words.
Pick just 2 or 3 words from today and make them yours: write what each one means in your own words, name the context clue or evidence that helped, then give one example from what you actually did in Clinical diagnosis team project. Try your own words first; the glossary is there if you get stuck. This is voluntary and counts as extra credit, so keep it short.
Saved on this device. Show Mr. Mendoza or add these to your notebook glossary to claim the extra credit.
Part 2 of 4 · Directions in plain English▸
2.1 Open your materials
Use the materials named in the first step below. Open lesson resources.
Practice newborn record (made-up practice data, not either class case and not a real baby)
History
- Baby girl, 2 days old, born at 39 weeks after an uncomplicated pregnancy.
- Feeding: breastfeeding every 2 to 3 hours; six wet diapers in the last day.
- Mother's blood type O positive; baby's blood type A positive.
Physical exam, day 2 of life
| Measurement or observation | Result | Unit | Range printed on this practice report |
|---|---|---|---|
| Weight | 3.1 | kg | 2.5 to 4.0 |
| Length | 49 | cm | 46 to 54 |
| Heart rate | 138 | beats per minute | 100 to 160 |
| Breathing rate | 46 | breaths per minute | 30 to 60 |
| Temperature | 36.9 | degrees C | 36.5 to 37.5 |
| Skin | Yellow color on the face and upper chest | observation | none printed |
Laboratory results, drawn at 48 hours of life
| Test | Result | Unit | Range printed on this practice report |
|---|---|---|---|
| Total bilirubin | 14.6 | mg/dL | below 12.0 at 48 hours |
| Hemoglobin | 17.2 | g/dL | 14.0 to 24.0 |
| Blood glucose | 62 | mg/dL | 50 to 90 |
Genetic screen
- Newborn screening panel: every condition on the panel reported as screen negative.
2.2 Start the work
As a team, define the SOP for reviewing a patient chart in a fixed order.
Show all 5 required steps
- As a team, define the SOP for reviewing a patient chart in a fixed order.
- Identify which variables in the chart are normal and which are out of range.
- Combine history, vitals, bloodwork, and genetics into a shared evidence table.
- Generate a ranked differential diagnosis and select the most likely candidate.
- Assign each member a section of the recommendation and note data limitations.
Lost your place? Confirm your team's fixed chart-review order, then get every out-of-range value into the shared evidence table before you rank the differential.
- 0-8 minAssign team roles: chart reviewer, vitals analyst, lab analyst, genetics reader.
- 8-15 minAgree on : order in which the team reviews each chart section.
- 15-40 minIndependent analysis by role; each member flags normal vs. out-of-range values.
- 40-58 minBuild shared evidence table; generate ranked as a group.
- 58-70 minSelect most likely candidate; each member drafts their recommendation section.
- 70-80 minEach member records one data limitation; team shares aloud before end of period.
- • Today you function as a clinical team, each role matters and each person's section feeds the final recommendation.
- • Real diagnostic teams use structured SOPs so nothing gets reviewed out of order or skipped.
- • Your evidence table is the shared document every team member writes to and reads from.
- • The limitation each person identifies is not optional: it shows the team where the diagnosis is still uncertain.
PLTW connection and today's work
In myPLTW, open Lesson 2.3 New to the Practice and go to Problem 2.3.1 A New Patient. Work it with your 2.3.1 sheet beside you: the newborn exam results are in myPLTW. If myPLTW will not open, build the table from the practice newborn record in Part 2 of this page.
Today's stopping point: Your workup notes should be taken. Today your platform work and evidence table should both be substantially complete.
PLTW activity titles identify the course connection. If your account will not open, use the posted materials for today and tell Mr. Mendoza. Do not mark an online activity complete unless you completed it.
Use the turn-in directions in Part 4 of this page. Do not create a second submission unless your teacher asks for one.
Show another explanation or a smaller first step
Need help? Choose a starting point
Part 3 of 4 · Worked example▸
This is a parallel case, not your own. Read it for the order of the work, then do your own in Part 4.
Team evidence table for a practice patient (an adult, not the newborn on your sheet):
- History: frequent thirst, frequent urination, family history of diabetes. Flag: relevant risk.
- Vital signs: BP 122/80 mmHg (stage 1 by the ACC/AHA bands, because the diastolic reads 80), pulse 78 bpm (normal).
- Bloodwork: fasting glucose 145 mg/dL (OUT OF RANGE, normal 70 to 99; 126 and above on two draws is the diabetes line), cholesterol 190 mg/dL (normal).
- Genetic screen: no single-gene flag.
Ranked differential: (1) Type 2 diabetes (top candidate, supported by high glucose plus classic symptoms and family history), (2) stress-related transient hyperglycemia (one draw only), (3) type 1 diabetes (less likely with gradual symptoms and this family pattern). Top candidate selected: Type 2 diabetes.
Each member owns one section; one stated limitation: only one glucose draw, so a repeat fasting test is needed.
| Component | Finding | In/Out of range |
|---|---|---|
| History | thirst, urination, family hx | risk present |
| Vitals | BP 122/80, pulse 78 | BP stage 1 (diastolic 80) |
| Bloodwork | glucose 145 mg/dL | OUT (normal 70-99) |
| Genetics | no single-gene flag | normal |
This model shows the level of evidence and organization needed to complete: A team-built evidence table combining all four workup components with out-of-range values flagged and a ranked differential diagnosis with the top candidate selected.
- Name the variables and include units.
- Enter observations without changing the raw values.
- Check labels, calculations, and patterns before interpreting the data.
Keep the structure. Replace the question, facts, measurements, and evidence. Then recheck units, vocabulary, and whether the conclusion goes beyond the evidence.
Also due today: Submit your team's evidence table and ranked differential as one PDF to Schoology assignment for this lesson in Schoology.
A smoke alarm detects signs of fire but can also react to burnt toast.
- What does the alarm detect?
- What creates a false alarm?
- What evidence is needed before declaring a fire?
A screening signal changes what to investigate next; it does not automatically prove the cause.
Biomedical tests have measured performance and biological sampling limits that a household alarm does not capture.
- • Alarm signal maps to a test result.
- • Burnt toast maps to a .
- • Inspection maps to confirmation or the next test.
Part 4 of 4 · Your work▸
Check your work before submitting
- Team produces a ranked differential grounded in the full data set.
- Each member contributes a documented section and identifies one limitation.
4.1 Turn in your work
DueCheck the Schoology assignment for this day- Hand in
- Shared team evidence table with all four workup components, flagged out-of-range values, and a ranked differential diagnosis with the top candidate selected.
How to submit and name your file
Submit your team's evidence table and ranked differential as one PDF to the Schoology assignment for this lesson in Schoology.
In Schoology, open your course and the assignment for this lesson. Attach your file, select Submit, and check that it appears in the submission.
PDF upload helpYou get two school days for every day you were absent, so this deadline moves with you.
Today's lesson is in Schoology
Each school day has one lesson page in Schoology that holds everything for the day: the goal, the story so far, every table and data value, the numbered steps, and what to turn in. Open it first and work from it. The other rows for this day, if any, are the score line for a paper quiz or test and the John Carroll debate item; they do not add work. Check Schoology for each deadline.
- Today's Lesson · Tue 11/10 · Wk12 · Pedigrees, then Punnett squares(today's lesson page: the goal, the data, the steps, and what to turn in are all on it)
Link will not open? Open Schoology, choose your course and section, and find the title shown above.
- CompleteEvery required part of the artifact is present, nothing left blank.
- AccurateThe science and the data are correct and match the evidence.
- Scientific reasoningYou explain your claim with evidence and reasoning (CER), not just an answer.
- Professional communicationClear, organized, labeled, and written the way a clinician or scientist would.
- SubmittedGo to Schoology to turn this in. Submit one PDF. Schoology attaches your name to your upload; on the page itself, write your period and code. Name the file: FirstName LastName - Assignment Title - YYYY-MM-DD.pdf. If you cannot get in, see Mr. Mendoza. Do not skip the work.
How this lesson connects
Keep using what you learned last class: A pedigree feeds parental genotypes into a Punnett square, so a family's history becomes a quantified probability instead of a rough estimate. Today: A team using a shared, ordered evidence table catches blind spots a lone reviewer misses, so combining people and data sources makes the diagnosis more accurate.
Practice: try a question, then check your answer▸
Claim ceiling for this check: Today's evidence supports a classroom claim about clinical diagnosis team project. It cannot prove causation, diagnose a real patient, or justify action outside this room.
Your evidence table shows an out-of-range value that supports two of your differential candidates equally. What should your team do before ranking one above the other?
Write an answer and pick a confidence to unlock the key.
Fast retrieval with instant answers, not the commit-then-reveal check above. Try each from memory first: write what you remember about the earlier units, then check yourself here.
Missed class or ready for more?▸
Optional practice for this unit's lab skills. Nothing in it is due today.
What today's skills lead to. These are real health-science careers this course builds toward. Tap one to see, on the US Department of Labor's O*NET site, what the job actually involves, what it pays, and how fast it is growing.
At home: open the results in myPLTW (Problem 2.3.1), or the practice newborn record on this page if myPLTW will not open. Build the evidence table following your 2.3.1 sheet, flag every value outside its printed range, rank a differential, and write which single condition the flagged values most support and why.
MedlinePlus: Lab TestsSubmit your team's evidence table and ranked differential as one PDF to the Schoology assignment for this lesson in Schoology.
Class still runs. Complete today's work as this page describes (it is self-guided). Need the concept taught without a teacher? Use this authoritative explainer:
NIH MedlinePlus Lab TestsSources: slides, readings, and resources▸
The deck carries the prior idea forward, lets you inspect an analogy, maps the rule to biology, and ends with the same evidence decision and exit ticket used on this page.
Hand-picked readings and interactives for this lesson, from authoritative open organizations and PLTW's own public course outline.
This week
My Progress dashboard